
Latest Blog Articles
Anabolic Steriod
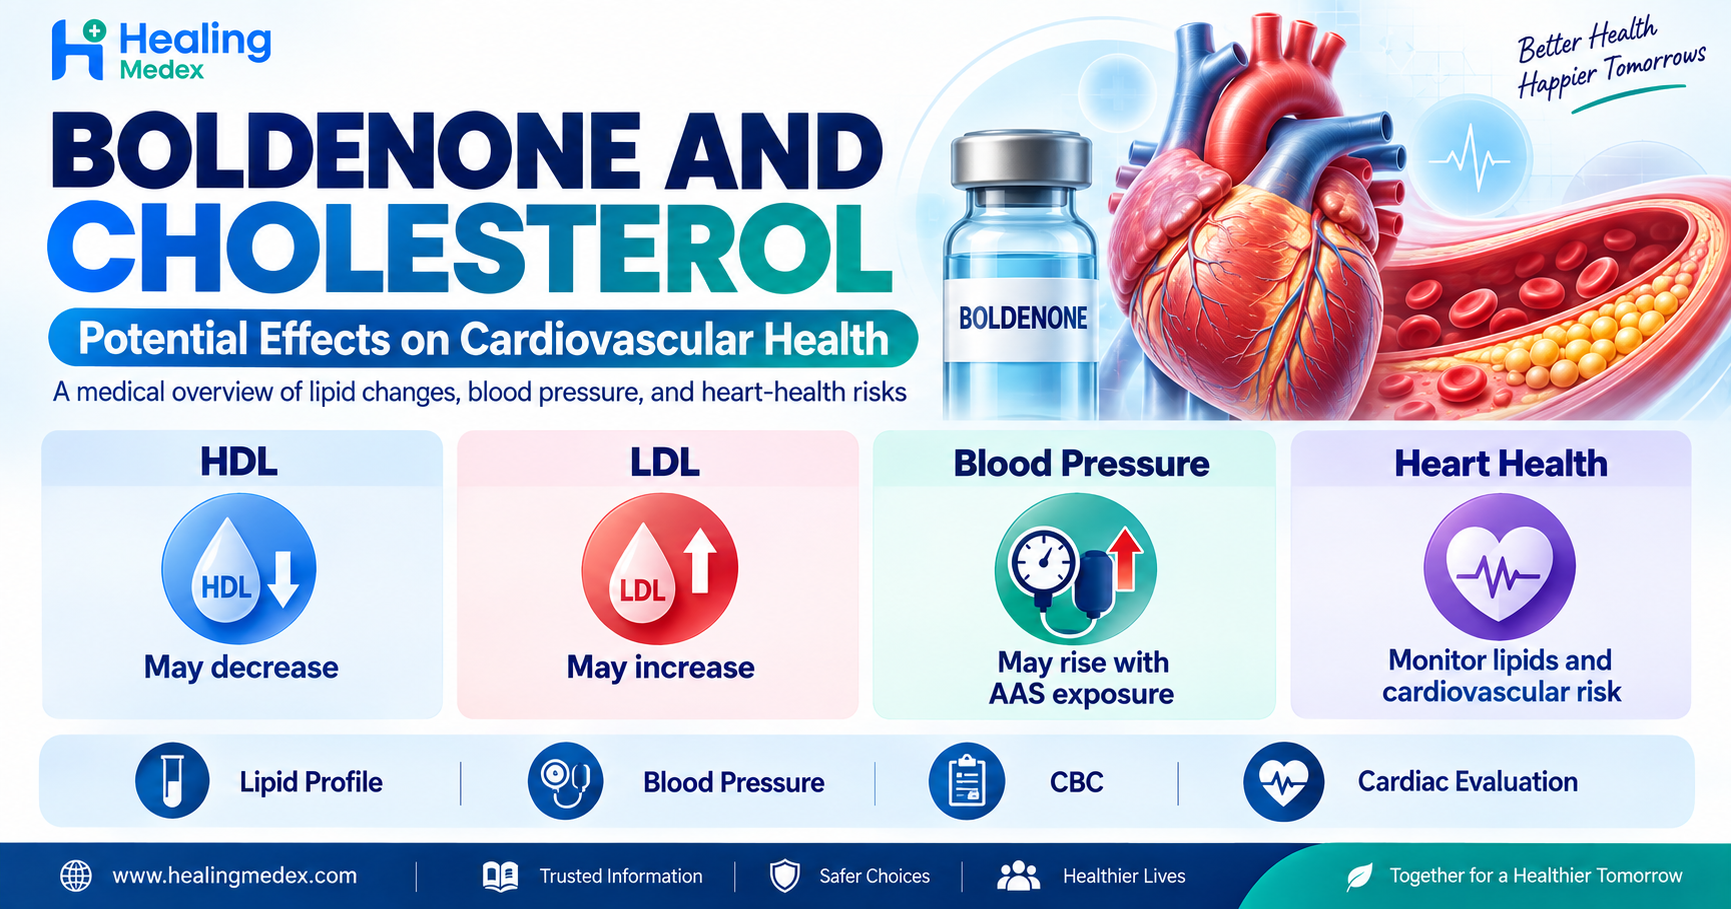
Boldenone and Cholesterol: Potential Effects on Cardiovascular Health
Boldenone is an anabolic-androgenic steroid (AAS) structurally related to testosterone. Boldenone undecylenate has primarily been used in veterinary medicine rather than as a standard human medical treatment. Despite this, non-medical use has occurred among some bodybuilders and athletes seeking increased muscle mass and performance. One important concern with boldenone and other anabolic steroids is their potential effect on cholesterol levels and cardiovascular health . Research specifically studying boldenone in humans is limited. Therefore, much of what is known about its cardiovascular risks comes from research involving anabolic-androgenic steroids as a broader group. Current evidence indicates that supraphysiological AAS exposure can adversely affect cholesterol, blood pressure, blood vessels and the structure and function of the heart. Understanding these effects is particularly important because cholesterol abnormalities may develop without obvious symptoms. What Is Boldenone? Boldenone is a synthetic androgen related to testosterone. One commonly encountered form is boldenone undecylenate , a long-acting ester generally administered by injection. Boldenone has anabolic and androgenic activity through activation of androgen receptors. Although it has historically been associated with veterinary applications, it has also been used non-medically for physique and performance enhancement. Human clinical safety data for such use are limited. This lack of high-quality human studies means it is not possible to precisely calculate how much cardiovascular risk comes from boldenone alone. However, cardiovascular concerns associated with the broader AAS class include: decreased HDL cholesterol increased LDL cholesterol increased blood pressure endothelial dysfunction increased red blood cell production changes in heart structure accelerated atherosclerosis increased risk of cardiovascular events These effects may become more important with prolonged exposure, high doses or simultaneous use of multiple anabolic steroids. How Could Boldenone Affect Cholesterol? Cholesterol travels through the bloodstream in particles known as lipoproteins. Two commonly measured forms are LDL cholesterol and HDL cholesterol . LDL is often called “bad cholesterol” because elevated concentrations contribute to cholesterol deposition inside artery walls. HDL is commonly called “good cholesterol” because it participates in transporting cholesterol away from peripheral tissues. Research involving anabolic-androgenic steroids consistently shows that supraphysiological androgen exposure can produce an unfavorable lipid profile. The exact response varies depending on the steroid, dose, duration of use, genetics, diet and other substances being taken. 1. HDL Cholesterol May Decrease One of the most consistently reported lipid effects of anabolic steroids is a reduction in HDL cholesterol. Low HDL is important because it often occurs together with other cardiovascular risk factors. Some AAS research has reported substantial HDL reductions during steroid exposure. However, these figures should not automatically be applied specifically to boldenone because direct controlled human boldenone studies are lacking. 2. LDL Cholesterol May Increase Anabolic steroid exposure has also been associated with increased LDL cholesterol. A 2025 systematic review and meta-analysis examining AAS users found a statistically significant average increase in LDL cholesterol compared with control groups. Higher LDL allows more cholesterol-containing particles to circulate in the bloodstream and potentially enter damaged arterial walls. Again, this evidence concerns AAS exposure overall and should not be interpreted as a precise measurement of boldenone's individual effect. 3. The LDL-to-HDL Balance May Become Less Favorable Cardiovascular risk cannot be understood from total cholesterol alone. A combination of: higher LDL + lower HDL can create a more atherogenic lipid profile. Over time, persistent unfavorable cholesterol levels may contribute to the development of atherosclerosis—the buildup of cholesterol-containing plaques within arteries. Why Are Cholesterol Changes Important? Atherosclerosis generally develops gradually. Cholesterol particles accumulate beneath the inner lining of arteries, triggering inflammation and plaque formation. As plaques enlarge, arteries may narrow and become less flexible. More importantly, some plaques can rupture. A ruptured coronary artery plaque can trigger formation of a blood clot that blocks blood flow to the heart muscle, resulting in a heart attack . Plaques affecting blood vessels supplying the brain can contribute to ischemic stroke . Recent cardiovascular reviews therefore increasingly recognize non-medical AAS exposure as an important cardiovascular risk factor, particularly among younger individuals who may otherwise appear healthy. Boldenone May Affect More Than Cholesterol Cholesterol abnormalities are only one potential component of cardiovascular risk. Increased Blood Pressure AAS users have demonstrated higher blood pressure in multiple studies. A 2025 meta-analysis found significant average increases in both systolic and diastolic blood pressure among AAS users compared with controls. High blood pressure increases stress on artery walls and forces the heart to work harder. When hypertension occurs together with high LDL and low HDL, cardiovascular risk may become greater. Changes in Red Blood Cell Levels Androgens can stimulate erythropoiesis—the production of red blood cells. Excessive increases can result in erythrocytosis , reflected by an abnormally high hematocrit. Higher hematocrit may increase blood viscosity and is another reason complete blood counts are commonly recommended when evaluating people exposed to supraphysiological androgens. Endothelial Dysfunction The endothelium is the thin layer of cells lining blood vessels. Healthy endothelial cells help arteries relax and regulate blood flow. Research suggests AAS exposure may interfere with endothelial function and normal nitric-oxide-mediated blood-vessel relaxation. These changes may contribute to hypertension and atherosclerosis. Changes in Heart Structure Long-term AAS exposure has also been associated with structural changes in the heart. A 2025 systematic review and meta-analysis involving approximately 2,000 men found that AAS-using resistance-trained athletes showed greater left-ventricular wall thickness and mass as well as modestly impaired measures of cardiac function compared with non-users. A newer 2026 systematic review has continued to examine duration-dependent cardiac changes associated with AAS exposure. These findings concern anabolic steroids broadly rather than boldenone alone. Can Boldenone Increase Heart-Attack Risk? There is not enough high-quality human research to assign boldenone itself a specific heart-attack risk percentage. However, the biological effects associated with supraphysiological anabolic-steroid exposure can create several conditions that favor cardiovascular disease: AAS exposure → abnormal cholesterol + higher blood pressure + vascular dysfunction + possible hematologic changes + cardiac remodeling Large observational and clinical studies have linked long-term AAS use with cardiovascular disease, accelerated atherosclerosis and adverse cardiac outcomes. Therefore, a normal appearance or high level of physical fitness should not be assumed to indicate normal cardiovascular health. Who May Be at Greater Risk? Potential cardiovascular risk may be higher in people who already have: elevated LDL cholesterol low HDL cholesterol hypertension diabetes or insulin resistance obesity smoking or nicotine exposure family history of premature heart disease existing cardiovascular disease high hematocrit kidney disease sleep apnea Risk may also increase with prolonged AAS exposure, high cumulative doses or simultaneous use of several performance-enhancing substances. Because non-medical users commonly combine multiple drugs, determining which individual steroid caused a particular abnormality can be difficult. What Tests Can Identify Cardiovascular Problems? Someone who has used anabolic steroids should be open with their healthcare professional about the substances involved. Clinical guidance for assessing AAS users recommends considering several measurements. Lipid Profile A lipid panel commonly includes: total cholesterol LDL cholesterol HDL cholesterol triglycerides This helps identify an atherogenic cholesterol pattern. Blood Pressure Blood pressure should also be measured because hypertension can occur without symptoms. Complete Blood Count A complete blood count can identify increased hemoglobin or hematocrit associated with excessive red blood cell production. Liver and Kidney Tests Liver and kidney function may also be evaluated because AAS use can affect multiple organ systems. Cardiac Evaluation Depending on exposure history, symptoms and cardiovascular risk, clinicians may consider investigations such as an electrocardiogram or echocardiogram. A 2025 cardiovascular review recommends considering lipid testing, complete blood count, liver testing, blood-pressure evaluation and echocardiography when assessing people using AAS. The exact tests required should be individualized by a healthcare professional. Do Cholesterol Levels Return to Normal After Stopping Anabolic Steroids? Some lipid abnormalities may improve after anabolic steroids are discontinued. Research suggests that reductions in HDL and elevations in LDL can be at least partly reversible in some users. However, recovery varies considerably between individuals. Recovery can depend on factors such as: duration of steroid exposure cumulative dose substances used genetics diet body composition smoking underlying metabolic disease Importantly, normalization of cholesterol does not necessarily prove that all cardiovascular effects have disappeared. Some research suggests structural or vascular abnormalities associated with prolonged AAS exposure may persist after discontinuation. Can Diet and Exercise Prevent Boldenone-Related Cholesterol Changes? A heart-healthy lifestyle remains important. This includes regular physical activity, avoiding smoking, maintaining an appropriate body weight and eating a diet rich in vegetables, fruits, whole grains, legumes, nuts and unsaturated fats while limiting trans fats and excessive saturated fat. However, healthy eating and exercise should not be considered protection against the cardiovascular effects of anabolic steroids . An individual may exercise intensively and appear extremely fit while still having high LDL, very low HDL, hypertension or structural cardiac changes. Laboratory testing and medical assessment are therefore more informative than physical appearance alone. Symptoms That Require Urgent Medical Attention Cardiovascular disease can initially produce no symptoms. However, emergency medical evaluation is needed for symptoms such as: new or severe chest pain or pressure sudden shortness of breath unexplained fainting severe or persistent palpitations sudden weakness or numbness on one side facial drooping difficulty speaking sudden severe dizziness These symptoms can indicate serious cardiovascular or neurological conditions and should not be ignored. Frequently Asked Questions 1. Does boldenone lower HDL cholesterol? Direct controlled human studies specifically examining boldenone are limited. However, reduced HDL is a well-established effect associated with supraphysiological exposure to many anabolic-androgenic steroids. Therefore, lipid monitoring is particularly relevant in people who have used boldenone or other AAS. 2. Can boldenone increase LDL cholesterol? Anabolic-androgenic steroids as a class have been associated with increased LDL cholesterol. There is insufficient human evidence to quantify precisely how much LDL would change with boldenone alone. 3. Is injectable boldenone safer for cholesterol than oral steroids? Being injectable does not eliminate cardiovascular risk. Although different AAS can have different effects on liver metabolism and lipids, injectable anabolic steroids can still contribute to dyslipidemia, hypertension, cardiac remodeling and other cardiovascular complications. 4. Can someone have cardiovascular problems despite feeling healthy? Yes. High LDL, low HDL, hypertension and early atherosclerosis frequently produce no symptoms. Blood tests and medical assessment may identify abnormalities long before symptoms develop. The Bottom Line Boldenone is an anabolic-androgenic steroid for which high-quality human safety research is limited. Much of our understanding of its potential cardiovascular effects therefore comes from broader research involving anabolic steroids. That research consistently raises concerns about lower HDL cholesterol, higher LDL cholesterol, elevated blood pressure, endothelial dysfunction, atherosclerosis and adverse changes in heart structure and function . The cardiovascular consequences of steroid exposure can also accumulate over time and may not always produce immediate symptoms. Anyone who has used boldenone or other anabolic steroids and is concerned about cardiovascular health should discuss their exposure openly with a qualified healthcare professional. A lipid profile, blood-pressure measurement, complete blood count and other cardiovascular investigations may be appropriate depending on the person's history and findings.
 Dr. Marcus Vance, PharmD

Anabolic Steriod
Clenbuterol: Is It an Anabolic Steroid? What You Should Know
What Is Clenbuterol? Clenbuterol is a long-acting beta-2 adrenergic receptor agonist . Beta-2 agonists stimulate receptors found in several tissues, particularly the smooth muscle surrounding the airways. Activation of these receptors can relax airway muscles, which is why clenbuterol has historically been used as a bronchodilator for asthma or other breathing disorders in some countries. Its pharmacological action is closer to other beta-2 agonist bronchodilators than to testosterone or anabolic steroids. Clenbuterol may also influence: Heart rate Blood pressure Energy expenditure Fat metabolism Blood glucose Blood potassium Skeletal muscle These systemic effects are one reason misuse can become dangerous. Is Clenbuterol an Anabolic Steroid? No. Clenbuterol is not an anabolic-androgenic steroid. Anabolic steroids such as testosterone, nandrolone, oxandrolone, stanozolol, and trenbolone primarily produce their effects through the androgen receptor . Clenbuterol instead works mainly by stimulating beta-2 adrenergic receptors . Therefore, although both clenbuterol and anabolic steroids may sometimes be discussed in bodybuilding communities, their mechanisms of action are fundamentally different. Clenbuterol vs Anabolic Steroids Feature Clenbuterol Anabolic Steroids Drug class Beta-2 adrenergic agonist Anabolic-androgenic steroid Testosterone derivative No Usually testosterone or steroid-related Main receptor Beta-2 adrenergic receptor Androgen receptor Originally developed for Bronchodilation Hormonal/medical indications vary May affect muscle tissue Potentially Yes Common non-medical purpose Fat loss/bodybuilding Muscle and strength enhancement Cardiovascular risks Yes Yes Testosterone suppression through typical androgenic feedback Not its primary mechanism Common with exogenous AAS This distinction is important because calling clenbuterol a "steroid" gives an inaccurate impression of how the substance actually works. Why Is Clenbuterol Sometimes Called an Anabolic Agent? There is an important difference between an anabolic steroid and an anabolic agent . Research in animals has demonstrated that clenbuterol can increase skeletal muscle mass and reduce fat under certain experimental conditions. Beta-2 receptor activation appears to contribute to these effects. However, findings from animal experiments cannot simply be translated into safe or effective bodybuilding use in humans. The World Anti-Doping Agency's 2026 Prohibited List places clenbuterol under S1.2 "Other Anabolic Agents." It is listed separately from S1.1 anabolic-androgenic steroids. So the most accurate description is: Clenbuterol is not an anabolic steroid , but it is classified as an anabolic agent in anti-doping regulations. Why Do Bodybuilders Use Clenbuterol? Non-medical clenbuterol use is commonly associated with attempts to: Reduce body fat Increase metabolic rate Preserve lean tissue during calorie restriction Achieve a more defined physique Improve perceived athletic performance Its stimulant-like metabolic effects have contributed to a reputation as a "fat burner." However, the evidence supporting meaningful performance-enhancing or bodybuilding benefits in humans is much less established than online claims often suggest. A systematic review examining reported clenbuterol adverse events among athletes found serious cardiovascular complications while also noting the lack of convincing evidence supporting its performance-enhancing usefulness. Potential physique changes therefore need to be weighed against potentially severe health consequences. Does Clenbuterol Burn Fat? Clenbuterol can stimulate adrenergic pathways involved in energy expenditure and fat metabolism. That biological effect is one reason it became popular in bodybuilding and weight-loss circles. However, this does not mean clenbuterol is a safe or medically appropriate weight-loss treatment. The doses and products used outside medical supervision can be unpredictable, and cardiovascular stimulation can occur alongside any metabolic effects. Poison Control notes that clenbuterol is frequently misused for possible fat-burning and anabolic effects despite serious toxicity being reported. Does Clenbuterol Build Muscle? This question requires more nuance. Animal research has demonstrated increases in skeletal muscle mass with clenbuterol exposure. These effects appear to involve beta-2 receptor stimulation rather than androgen-receptor activation. But strong evidence demonstrating that clenbuterol safely produces meaningful muscle growth in humans is lacking. Consequently, animal findings should not be interpreted as proof that clenbuterol is an effective or safe muscle-building drug for people. What Are the Common Side Effects of Clenbuterol? Because clenbuterol stimulates the adrenergic nervous system, side effects may include: Rapid heartbeat Heart palpitations Tremor or shaking Anxiety or restlessness Sweating Headache Nausea Muscle cramps Changes in blood pressure It may also produce important metabolic abnormalities such as low potassium levels (hypokalemia) and elevated blood glucose (hyperglycemia) . The intensity of these effects can vary substantially between individuals. Can Clenbuterol Affect the Heart? Cardiovascular complications are among the biggest concerns surrounding clenbuterol misuse. Published reports have associated clenbuterol exposure with: Persistent tachycardia Supraventricular tachycardia Atrial fibrillation Abnormal blood pressure Chest pain Myocardial ischemia Myocardial injury Cardiomyopathy Heart attack Cardiac arrest A 2023 systematic review of athlete case reports found cardiac complications to be particularly prominent among reported serious adverse events. These complications can occur even in relatively young or apparently healthy individuals. Can Clenbuterol Lower Potassium? Yes. Beta-2 receptor stimulation can shift potassium from the bloodstream into cells, causing hypokalemia . Low potassium may contribute to: Muscle weakness Muscle cramps Palpitations Abnormal heart rhythms Clenbuterol toxicity reports frequently describe hypokalemia together with tachycardia and hyperglycemia. This combination can place additional stress on the cardiovascular system. Does Clenbuterol Suppress Natural Testosterone? Clenbuterol does not work through the androgen receptor in the same way as anabolic-androgenic steroids. Therefore, it should not automatically be assumed to cause the same direct hypothalamic-pituitary-gonadal suppression associated with exogenous testosterone or anabolic steroid exposure . However, many people who misuse clenbuterol also use anabolic steroids or other performance-enhancing drugs simultaneously. This makes hormone changes difficult to attribute to clenbuterol itself. Using multiple substances can also increase overall health risk. Is Clenbuterol Approved for Human Use? Regulatory status differs between countries. In the United States, clenbuterol is not FDA-approved for human use . The FDA does list an approved clenbuterol hydrochloride veterinary product, Ventipulmin, for horses. Clenbuterol has been used or approved as a bronchodilator for humans in some countries outside the United States. People should therefore check the regulations that apply in their own country rather than assuming that online availability means a product is medically approved. Is Clenbuterol Banned in Sports? Yes, under World Anti-Doping Agency rules. The 2026 WADA Prohibited List includes clenbuterol under S1.2 Other Anabolic Agents . Competitive athletes should therefore be particularly cautious about products claiming to contain clenbuterol or supplements that could potentially be contaminated with prohibited substances. Is Clenbuterol Safer Than Anabolic Steroids? It is not useful to assume that clenbuterol is safe simply because it is not technically a steroid. The substances produce different risk profiles. Anabolic steroids may cause hormonal suppression, fertility problems, lipid abnormalities, cardiovascular changes, liver effects depending on the compound, and other androgen-related complications. Clenbuterol can produce intense adrenergic and cardiovascular stimulation and potentially dangerous metabolic abnormalities. In other words: Different mechanism does not mean lower risk. Both categories can cause serious harm when misused. What Are the Signs of Possible Clenbuterol Toxicity? Potential warning signs include: Very rapid or irregular heartbeat Severe palpitations Chest pain Fainting Severe tremor Shortness of breath Confusion or severe agitation Seizure Severe weakness Serious toxicity has been associated with myocardial injury, arrhythmias, cardiogenic shock, seizures, and cardiac arrest. Someone experiencing severe symptoms after suspected clenbuterol exposure should seek urgent medical attention rather than trying to manage the problem independently . Frequently Asked Questions 1.Is clenbuterol a steroid? No. Clenbuterol is a beta-2 adrenergic agonist, not an anabolic-androgenic steroid. 2.Is clenbuterol anabolic? It has demonstrated anabolic effects in animal studies and is categorized by WADA as an "other anabolic agent." That does not make it an anabolic steroid or establish safe muscle-building benefits in humans. 3.Is clenbuterol a fat burner? Clenbuterol can influence metabolic and fat-mobilizing pathways, which explains its non-medical use for weight loss. However, it is not a harmless fat-burning supplement, and serious cardiovascular toxicity has been reported. 4.Is clenbuterol the same as testosterone? No. Testosterone is an androgenic steroid hormone that acts primarily through androgen receptors. Clenbuterol stimulates beta-2 adrenergic receptors. 5.Can clenbuterol cause heart problems? Yes. Tachycardia, arrhythmias, myocardial injury, cardiomyopathy, heart attack, and cardiac arrest have all been reported in association with clenbuterol exposure. 6.Is clenbuterol permitted for competitive athletes? Clenbuterol appears on the WADA 2026 Prohibited List under Other Anabolic Agents. Final Takeaway Clenbuterol is not an anabolic steroid. It is a beta-2 adrenergic agonist with pharmacological effects that are very different from testosterone and traditional anabolic-androgenic steroids. Its ability to influence metabolism and skeletal muscle has led to its misuse for bodybuilding, fat loss, and performance enhancement. These potential effects have also led WADA to classify clenbuterol as an "other anabolic agent." But the distinction between a steroid and a non-steroid should not be confused with safety. Clenbuterol has been associated with rapid heartbeat, arrhythmias, abnormal potassium and glucose levels, myocardial injury, cardiomyopathy, heart attack, and other potentially life-threatening complications. Anyone considering or already using performance-enhancing substances should discuss their health, medications, cardiovascular risk factors, and laboratory monitoring with a qualified healthcare professional.
Dr. Marcus Vance, PharmD
Anabolic Steriod
Testosterone vs Nandrolone: What Are the Medical and Hormonal Differences?
Testosterone and nandrolone are both anabolic-androgenic hormones, but they are not medically or hormonally equivalent . Testosterone is the principal natural androgen in men and is used medically as replacement therapy in appropriately diagnosed testosterone deficiency. Nandrolone is a synthetic derivative of testosterone—specifically 19-nortestosterone —with a different pattern of androgenic, anabolic and hormonal activity. Although both substances activate androgen receptors and can suppress the body's own hormone production, important differences exist in their effects on DHT, estrogen pathways, progesterone receptors, fertility, red blood cell production and other tissues . This article explains the major medical and hormonal differences between testosterone and nandrolone. Testosterone vs Nandrolone: Quick Comparison Feature Testosterone Nandrolone Type Naturally occurring androgen Synthetic 19-nortestosterone androgen Main medical role Testosterone replacement in diagnosed hypogonadism Certain anabolic medical indications; these vary by country Androgen receptor activity Strong Strong Conversion by 5-alpha-reductase Converts to potent DHT Converts to less androgenically active dihydronandrolone Estrogen pathway Readily aromatized to estradiol Less susceptible to aromatization; estrogenic metabolism is more complex Progestogenic activity Relatively limited More significant progesterone-receptor activity Natural testosterone suppression Yes Yes Sperm suppression Possible/significant Possible/significant Red blood cell effects Can increase hematocrit Can increase hemoglobin/red-cell mass Lipid effects Requires cardiovascular-risk monitoring May lower HDL and increase LDL Appropriate substitute for TRT? Testosterone itself is the standard replacement hormone Not considered a routine substitute for testosterone replacement 1. What Is Testosterone? Testosterone is the major androgen produced primarily by the testes. Smaller amounts are also produced by the adrenal glands. It plays important roles in: Sexual development Libido and sexual function Sperm production Muscle and bone maintenance Red blood cell production Secondary male sexual characteristics General androgen-dependent tissue function Medical testosterone therapy is used when a patient has an appropriate clinical diagnosis of testosterone deficiency. The Endocrine Society emphasizes that hypogonadism should not be diagnosed from symptoms alone. Diagnosis involves compatible symptoms or signs together with consistently low, accurately measured testosterone concentrations and evaluation of the underlying cause. 2. What Is Nandrolone? Nandrolone is an anabolic-androgenic steroid closely related chemically to testosterone. It is often called 19-nortestosterone because its chemical structure lacks the carbon-19 methyl group found in testosterone. This relatively small structural change alters how the hormone behaves in different tissues. Nandrolone still activates androgen receptors, but its metabolism differs substantially from testosterone. Medical indications and availability vary internationally. In current U.S. labeling, nandrolone decanoate is indicated for management of anemia associated with renal insufficiency , because it can increase hemoglobin and red blood cell mass. It should not be assumed that nandrolone is approved for every condition for which it has historically been studied. 3. Testosterone Is Primarily a Replacement Hormone One of the largest medical differences concerns why the drugs are prescribed. For men with appropriately diagnosed hypogonadism, testosterone therapy aims to restore testosterone exposure and improve consequences of androgen deficiency. The Endocrine Society continues to describe physiologic testosterone replacement as having established benefits for men with properly diagnosed hypogonadism caused by disorders involving the testes, hypothalamus or pituitary gland. Nandrolone, despite being an androgen, does not reproduce every physiological action of testosterone in the same way. Therefore: Nandrolone should not automatically be regarded as an alternative form of TRT. Its tissue metabolism, estrogenic activity and progestogenic activity differ from testosterone. 4. Testosterone Produces DHT — Nandrolone Behaves Differently This is one of their most important hormonal differences. The enzyme 5-alpha-reductase converts testosterone into dihydrotestosterone, or DHT. DHT has stronger androgenic activity than testosterone in several androgen-sensitive tissues. This pathway is especially important in tissues such as the prostate and skin. Nandrolone also undergoes 5-alpha-reduction, but the result is very different. Instead of producing DHT, nandrolone produces 5-alpha-dihydronandrolone , sometimes called DHN. Unlike DHT, this nandrolone metabolite has weaker androgen-receptor activity than its parent hormone. Experimental pharmacology therefore helps explain why nandrolone demonstrates proportionally less androgenic activity in certain tissues compared with its anabolic effects. This does not mean nandrolone has no androgenic effects. Androgenic adverse effects remain possible. 5. Nandrolone Has a Different Anabolic-to-Androgenic Profile Both testosterone and nandrolone activate the androgen receptor. However, historical laboratory and animal assays show nandrolone having a higher ratio of muscle-related anabolic activity relative to androgenic activity than testosterone. This distinction is frequently misunderstood. These experimental ratios are not clinical conversion formulas and should not be used to calculate equivalent doses or design non-medical steroid regimens. Humans also respond differently depending on dose, exposure, health status, genetics and concurrent medications. 6. Testosterone Has a More Established Estradiol Pathway Some testosterone is converted through the enzyme aromatase into estradiol . Estradiol is not simply a "female hormone." In men, normal estrogen signaling contributes to areas such as: Bone health Sexual physiology Neuroendocrine signaling Reproductive hormone regulation Nandrolone is structurally different and appears to be less susceptible than testosterone to conventional aromatization. Research into its exact estrogenic metabolism in humans is less complete, and older human research has demonstrated changes in estrogen metabolites during nandrolone exposure. For this reason, it is too simplistic to describe nandrolone as simply having "no estrogen effects." Hormonal effects need to be interpreted clinically rather than predicted from one pathway alone. 7. Nandrolone Has More Relevant Progestogenic Activity Another important difference involves the progesterone receptor . Nandrolone is not only an androgen-receptor agonist. Laboratory evidence shows significant progestogenic activity through the progesterone receptor. Testosterone does not have the same clinically relevant progestogenic profile. This matters because progesterone-receptor signaling can influence hypothalamic and pituitary regulation of reproductive hormones. Consequently, nandrolone's endocrine effects cannot be understood simply by looking at serum testosterone or estrogen concentrations. 8. Both Can Suppress Natural Testosterone Production Taking an external androgen tells the hypothalamus and pituitary that sufficient androgenic signaling is already present. This can reduce signaling through the hypothalamic-pituitary-gonadal axis and decrease stimulation of the testes. Nandrolone labeling specifically notes that anabolic steroids suppress pituitary gonadotropic function and may directly affect the testes. Testosterone therapy can also suppress the reproductive axis. Therefore, someone receiving external testosterone may have an adequate circulating testosterone concentration while producing considerably less testosterone inside the testes. The same general principle applies to nandrolone. 9. Both Can Reduce Fertility Suppression of LH and FSH can reduce intratesticular testosterone concentrations and interfere with sperm production. FDA testosterone prescribing information warns that exogenous androgen administration may lead to azoospermia , meaning an absence of sperm in the semen. Because of this effect, the Endocrine Society recommends against beginning testosterone therapy in men who are planning fertility in the near term. Nandrolone also suppresses pituitary-gonadal function and may adversely affect testicular function. Anyone concerned about fertility should discuss this before beginning androgen therapy rather than waiting until fertility problems develop. 10. Their Effects on Sexual Function Are Not Identical Testosterone deficiency itself can contribute to reduced libido and certain sexual symptoms, so appropriately prescribed testosterone replacement may improve some symptoms in genuinely hypogonadal patients. The effects of nandrolone are more complicated. Because nandrolone can suppress endogenous testosterone while producing different DHT, estrogen and progesterone-receptor effects, sexual symptoms during non-medical nandrolone exposure cannot reliably be predicted from total testosterone measurements alone. Possible sexual symptoms should not automatically be blamed on one hormone such as estrogen or prolactin without testing and clinical assessment. Other contributors may include: Cardiovascular health Psychological factors Medication use Other endocrine abnormalities Relationship factors Sleep disorders Diabetes Blood pressure General health 11. Both Can Increase Red Blood Cell Production Androgens stimulate erythropoiesis—the production of red blood cells. Testosterone therapy can therefore increase hemoglobin and hematocrit. Monitoring hematocrit is an important component of medical testosterone therapy, particularly because excessive elevation may require reassessment of treatment. Nandrolone has sufficiently strong erythropoietic effects that its U.S. labeling includes treatment of anemia caused by renal insufficiency. This illustrates an important principle: A drug's ability to increase red blood cells can be medically useful in one context but potentially problematic in another. 12. Cardiovascular and Cholesterol Effects Matter Neither drug should be considered harmless to cardiovascular health. Nandrolone labeling reports that anabolic steroids can: Increase LDL cholesterol Decrease HDL cholesterol Such changes can make the lipid profile less favorable. Testosterone safety information has also changed in recent years. Following review of the large TRAVERSE trial and post-market blood-pressure studies, the FDA removed older boxed-warning language concerning increased major cardiovascular events from testosterone products but required warnings about increased blood pressure across the testosterone drug class. In 2026, the FDA reported that the TRAVERSE trial found no meaningful difference in major cardiovascular events between testosterone gel and placebo in the studied population, while testosterone treatment continues to require individualized assessment and monitoring. These findings should not be extrapolated to high-dose non-medical testosterone or anabolic-steroid use. 13. Does Nandrolone Cause Fewer Androgenic Side Effects? Pharmacologically, nandrolone can demonstrate lower androgenic activity in some tissues because 5-alpha-reduction produces the weaker androgen dihydronandrolone rather than DHT. However, lower androgenic activity does not mean zero androgenic activity or lower overall health risk . Nandrolone remains an anabolic-androgenic steroid. Potential concerns with anabolic steroid exposure can include effects involving: Reproductive hormone suppression Fertility Cholesterol Cardiovascular health Blood pressure and fluid retention Red blood cell production Skin and hair Mood or psychological symptoms Sexual function Risk also changes considerably with dose, duration, underlying disease and whether multiple anabolic steroids are being used. 14. Is Nandrolone Safer Than Testosterone? There is no universal answer because the two drugs are used for different medical purposes and have different physiological effects. For a person with appropriately diagnosed testosterone deficiency, the therapeutic goal is generally to replace the deficient hormone with testosterone , not to select an anabolic steroid according to which appears more anabolic or less androgenic. The evidence base supporting contemporary testosterone replacement is also substantially larger than the evidence supporting nandrolone as a general treatment for male hypogonadism. A review of nandrolone's possible therapeutic applications has specifically noted that human evidence remains limited in several proposed areas and that additional research is required. Testosterone vs Nandrolone: The Main Hormonal Differences The comparison can be summarized simply: Testosterone Is the body's major natural androgen Converts to DHT Aromatizes to estradiol Is the standard replacement hormone for appropriately diagnosed male hypogonadism Suppresses LH, FSH and sperm production when administered externally Can increase hematocrit and blood pressure Nandrolone Is a synthetic 19-nortestosterone derivative Converts to the less androgenically active dihydronandrolone Has a different and less straightforward estrogenic pathway Has significant progestogenic activity Has relatively greater anabolic versus androgenic activity in experimental models Suppresses the reproductive hormone axis Can affect fertility and lipid levels Has medical indications that differ from testosterone What Monitoring May Be Needed With Androgen Therapy? Monitoring depends on the specific drug, indication, age, medical history and national prescribing guidance. For medically prescribed testosterone, clinicians may consider factors such as: Testosterone concentrations Hemoglobin and hematocrit Blood pressure Treatment response and adverse effects Prostate assessment when clinically appropriate Cardiovascular risk Fertility plans Additional testing based on the underlying cause of hypogonadism Current endocrine guidance emphasizes both confirming the diagnosis before starting therapy and monitoring patients after treatment begins. Final Takeaway Testosterone and nandrolone belong to the same broad anabolic-androgenic steroid family, but their hormonal effects are meaningfully different. Testosterone is the body's natural primary androgen and is the established replacement hormone for appropriately diagnosed testosterone deficiency. Nandrolone is a synthetic 19-nortestosterone compound with a higher relative anabolic profile, weaker androgenic activity in some tissues, different estrogen metabolism and meaningful progesterone-receptor activity. Both can suppress natural testosterone and sperm production, and both can produce medically important systemic effects. For these reasons, nandrolone should not be viewed as a simple substitute for testosterone, and choosing between androgen therapies should be based on a confirmed medical diagnosis, approved indications, individual health risks and clinician monitoring—not bodybuilding comparisons or anabolic-to-androgenic ratios. Frequently Asked Questions 1. Is nandrolone the same as testosterone? No. Nandrolone is structurally related to testosterone but is a synthetic 19-nortestosterone derivative with different metabolism and tissue effects. 2.Does nandrolone suppress natural testosterone? Yes. Nandrolone and other anabolic steroids can suppress pituitary gonadotropin signaling and reduce endogenous testicular hormone production. 3.Does testosterone suppress sperm production? Yes. External testosterone can suppress the reproductive axis and may cause severe reductions in sperm production or azoospermia. 4.Does nandrolone convert to DHT? Not in the same way as testosterone. Testosterone is converted to DHT, whereas nandrolone is converted by 5-alpha-reductase to dihydronandrolone, which has weaker androgenic activity than nandrolone itself. 5.Can nandrolone replace testosterone in TRT? Nandrolone is not considered a routine equivalent replacement for testosterone. Testosterone remains the standard hormone used to replace deficient testosterone in appropriately diagnosed male hypogonadism.
Dr. Marcus Vance, PharmD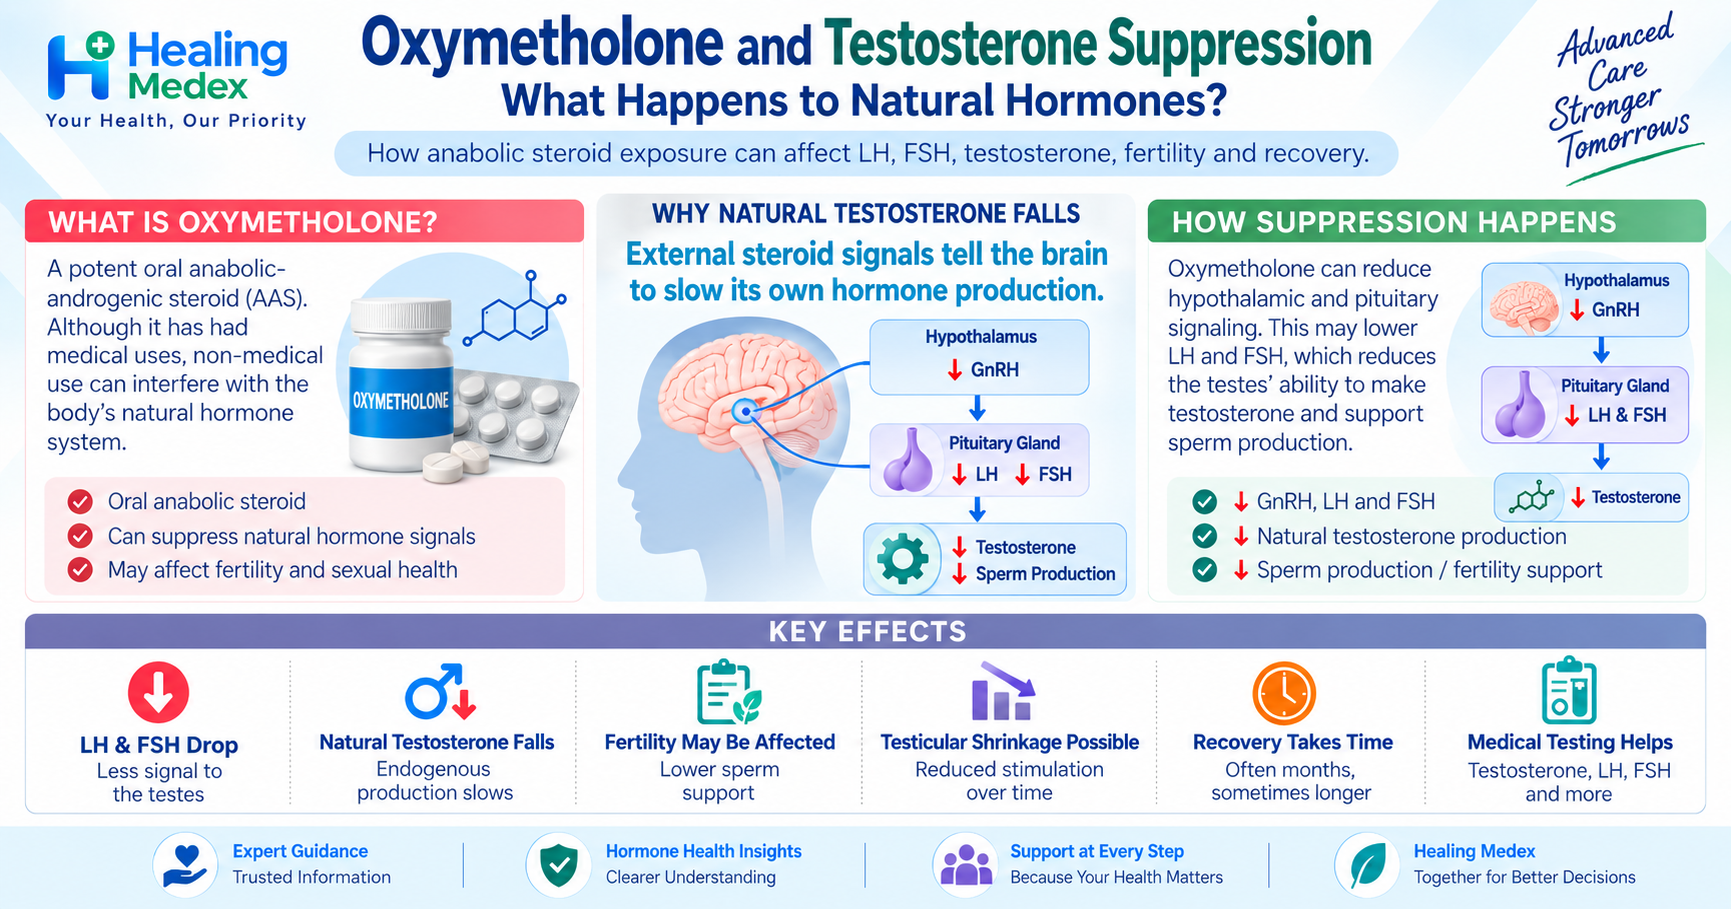
Anabolic Steriod
Oxymetholone and Testosterone Suppression: What Happens to Natural Hormones?
Oxymetholone, commonly known by the former brand name Anadrol , is a potent oral anabolic-androgenic steroid (AAS). Although it has had legitimate medical uses for certain types of anemia, oxymetholone is also used non-medically for physique and performance purposes. One important consequence of anabolic steroid exposure is often misunderstood: having more androgen activity in the body does not mean the testes continue producing normal amounts of testosterone . In fact, oxymetholone and other anabolic-androgenic steroids can suppress the hormonal signals responsible for natural testosterone production. This may affect testosterone levels, testicular function, sperm production, fertility, sexual health and mood. Suppression can become particularly noticeable after the steroid is discontinued. This article explains what happens to the body's natural hormones, why testosterone can fall, and what recovery may look like after anabolic steroid exposure. What Is Oxymetholone? Oxymetholone is an oral anabolic-androgenic steroid . It was developed medically to stimulate red blood cell production in certain forms of anemia. Like other anabolic steroids , however, oxymetholone produces androgenic signals that can interfere with the body's normal reproductive hormone system. Product information for oxymetholone has identified effects such as inhibition of testicular function, testicular atrophy and oligospermia , meaning a reduced sperm concentration. The hormonal consequences are especially relevant when oxymetholone is used outside medical supervision. How Does the Body Normally Produce Testosterone? Natural testosterone production depends on a communication system called the hypothalamic-pituitary-gonadal axis , or HPG axis. It works through three main steps: 1. The hypothalamus releases GnRH The brain releases gonadotropin-releasing hormone (GnRH). 2. The pituitary gland releases LH and FSH GnRH signals the pituitary gland to release two important hormones: LH — luteinizing hormone FSH — follicle-stimulating hormone 3. The testes respond LH stimulates Leydig cells in the testes to produce testosterone. FSH, together with high concentrations of testosterone within the testes, helps support sperm production. When this system is functioning normally, the brain constantly adjusts hormone production through a feedback mechanism. How Does Oxymetholone Suppress Natural Testosterone? Introducing powerful external anabolic-androgenic steroids changes this feedback system. The brain detects strong androgenic signals and essentially receives the message that sufficient androgen is already present. As a result, the hypothalamus and pituitary can reduce their hormonal signaling. This may lead to: Reduced GnRH → reduced LH and FSH → reduced testicular testosterone production. Suppression of GnRH, LH and FSH is a central mechanism behind anabolic steroid-induced hypogonadism (ASIH) . Therefore, someone can have substantial androgenic activity from an anabolic steroid while simultaneously producing very little testosterone naturally. What Happens to LH? LH is one of the most important hormones controlling testosterone production. When anabolic steroid exposure suppresses pituitary activity, LH can fall significantly . Lower LH means that the Leydig cells inside the testes receive less stimulation to manufacture testosterone. If suppression continues, endogenous—or naturally produced—testosterone can become very low. This explains why testosterone production may not immediately return to normal when anabolic steroids are discontinued. The brain-pituitary-testicular signaling pathway first has to reactivate. What Happens to FSH? FSH is especially important for reproductive function. Together with testosterone inside the testes, FSH supports the Sertoli cells responsible for sperm development. Suppression of FSH may therefore contribute to: Reduced sperm production Low sperm concentration Poorer fertility Severe oligospermia In some cases, azoospermia, where no sperm are detected in the ejaculate Exogenous testosterone and anabolic-androgenic steroids are well documented to suppress the HPG axis and reduce intratesticular testosterone, which can substantially interfere with spermatogenesis. Can the Testes Become Smaller? Yes. When LH and FSH remain suppressed, the testes receive less stimulation. Some anabolic steroid users may develop reduced testicular volume or testicular atrophy . Oxymetholone product information has specifically listed inhibition of testicular function and testicular atrophy among potential adverse effects. Testicular size can improve after normal hormone signaling returns, but recovery varies considerably between individuals. What Happens While Oxymetholone Is Being Used? Natural testosterone may already be suppressed while the person is taking an anabolic steroid. However, symptoms of low natural testosterone may not always be immediately obvious because the anabolic steroid itself continues producing androgenic effects. This creates an important distinction: Androgen activity in the body is not the same thing as normal natural testosterone production. A person may therefore feel relatively normal—or notice strong anabolic effects—while LH, FSH and endogenous testosterone production are substantially suppressed. The consequences can become much more noticeable when the external androgen is removed. What Can Happen After Oxymetholone Is Stopped? After anabolic steroid exposure stops, external androgen activity declines. Natural testosterone production, however, may not immediately restart at the same speed. This temporary mismatch can result in a period of post-anabolic-steroid hypogonadism . Possible symptoms include: Low energy Fatigue Reduced libido Erectile difficulties Depressed or low mood Anxiety or irritability Reduced motivation Loss of strength Reduced muscle mass Increased body fat Testicular shrinkage Reduced sperm production Fertility problems Withdrawal from chronic AAS use has also been associated with anxiety and depressive symptoms in some individuals. Persistent or severe mood symptoms should be assessed by a healthcare professional. Does Oxymetholone Affect Fertility? It can. Normal sperm production requires active signaling from LH and FSH and sufficiently high testosterone concentrations inside the testes . Anabolic steroids can suppress all three. Oxymetholone labeling has specifically identified oligospermia as a potential adverse effect , and broader AAS research shows that suppression can sometimes progress to extremely low sperm counts or azoospermia. This is especially important for men who are planning to have children. Normal testosterone in a blood test also does not necessarily guarantee normal sperm production. A semen analysis provides more direct information about fertility. How Long Does Natural Testosterone Take to Recover? There is no single recovery timeline. Recovery can depend on factors such as: Duration of anabolic steroid exposure Total lifetime exposure Types of steroids used Whether several anabolic steroids were combined Age Baseline hormone function Previous steroid exposure Individual biology Other medical conditions A 2023 scoping review found that recovery from anabolic steroid-induced hypogonadism is highly variable. Across the available evidence, gonadotropins such as LH and FSH often recovered over approximately 3–6 months , while testosterone recovery generally occurred over months but could remain incomplete in some individuals. Other clinical reviews have reported that many men with shorter periods of AAS exposure recover normal HPG-axis function within a year after stopping, although this should not be considered a guarantee for an individual patient. Can Testosterone Suppression Last Longer Than Expected? Yes. Most people should not assume that natural hormone production will automatically return to normal within a particular number of weeks. Research has documented individuals with prolonged symptoms and biochemical evidence of hypogonadism after anabolic steroid cessation. The likelihood and duration appear to vary substantially. Longer or heavier exposure may be associated with slower recovery, although predicting recovery for one individual remains difficult. Persistent symptoms should therefore be investigated rather than automatically attributed to a temporary hormonal "crash." How Long Does Fertility Take to Recover? Sperm production can recover more slowly than blood testosterone. Research into anabolic steroid-induced hypogonadism suggests that spermatogenesis may require months and sometimes considerably longer to recover . Testicular volume may also recover over months to years in some individuals. Men concerned about future fertility should discuss their history openly with an endocrinologist, urologist or reproductive specialist. Which Blood Tests May Be Helpful? Someone with symptoms following anabolic steroid use should receive an individualized medical assessment rather than relying only on how they feel. Depending on the situation, a clinician may consider tests such as: Morning total testosterone Repeat morning testosterone when appropriate LH FSH SHBG Calculated or measured free testosterone when indicated Estradiol Prolactin Complete blood count/hematocrit Liver function tests Lipid profile A semen analysis may also be appropriate when fertility is a concern. Clinical guidelines recommend diagnosing testosterone deficiency based on both compatible symptoms and consistently low testosterone concentrations, usually confirmed with repeat morning measurements. Because oxymetholone can affect organs beyond the reproductive system, hormone testing should not necessarily be the only medical evaluation performed. Oxymetholone Can Affect More Than Testosterone Although testosterone suppression is important, it is not the only potential concern associated with oxymetholone. As an orally active anabolic steroid, oxymetholone has also been associated with significant adverse effects involving areas such as: Liver function Cholesterol levels Fluid retention Blood pressure Red blood cell levels Fertility Cardiovascular health Oxymetholone and other 17-alpha-alkylated oral anabolic steroids have particular concerns regarding liver toxicity. For this reason, focusing only on whether testosterone eventually recovers may overlook other important health risks. What About “PCT” After Oxymetholone? Some non-medical anabolic steroid users attempt to restart natural testosterone production with so-called post-cycle therapy (PCT) . However, self-directed PCT is not a standardized medical treatment. Drugs sometimes used for this purpose can have their own adverse effects, interactions and contraindications, and products obtained outside regulated pharmacies may be counterfeit or contain unexpected ingredients. Medical literature discusses several therapies that specialists may use for selected patients with persistent AAS-related hypogonadism or infertility, but the evidence base remains limited and treatment depends strongly on the individual's hormone results, fertility goals and medical history. Anyone experiencing prolonged hormonal symptoms should therefore seek medical assessment rather than assuming a standard online PCT protocol is appropriate. When Should You Speak to a Doctor? Medical evaluation is particularly important when someone experiences: Persistent low libido Erectile dysfunction Severe fatigue Significant mood changes Depression Testicular shrinkage Fertility problems Persistently low testosterone Abnormal liver tests Jaundice Significant swelling or fluid retention Severe depression, suicidal thoughts, jaundice, chest pain or other serious symptoms require urgent medical attention. Being open with the clinician about previous anabolic steroid exposure can make diagnosis considerably easier. Key Takeaway Oxymetholone can suppress natural testosterone production by reducing activity within the hypothalamic-pituitary-gonadal axis. As LH and FSH decline, the testes receive less stimulation to produce testosterone and sperm. This can contribute to low endogenous testosterone, reduced testicular volume and impaired fertility. After oxymetholone or other anabolic steroids are discontinued, natural hormone production may recover—but the timeline varies widely. Testosterone and gonadotropin recovery can take months, while fertility may take longer, and some individuals experience prolonged hypogonadism. Anyone with persistent symptoms should consider proper medical evaluation and hormone testing rather than attempting to diagnose or treat hormone suppression based solely on symptoms. Frequently Asked Questions 1. Does oxymetholone shut down natural testosterone? Oxymetholone can significantly suppress the hormonal signaling responsible for natural testosterone production. The degree of suppression varies between individuals. 2.Does testosterone immediately return after stopping oxymetholone? Not necessarily. The hypothalamus, pituitary gland and testes may need time to restore normal communication. Recovery may take months and can occasionally be prolonged. 3.Can oxymetholone reduce sperm count? Yes. Oligospermia has been reported with oxymetholone, and suppression of LH, FSH and intratesticular testosterone from anabolic steroids can impair sperm production. 4.Can anabolic steroid-related testicular shrinkage recover? Recovery is possible, but the timing varies. Research on AAS-induced hypogonadism suggests that testicular volume may improve gradually over months or longer. 5.Which hormones are most affected by anabolic steroids? The major hormones involved include GnRH, LH, FSH and endogenous testosterone. Sperm production can also be affected because of reduced gonadotropin signaling and intratesticular testosterone. 6.Can testosterone suppression become permanent? Persistent hypogonadism has been documented, although it is difficult to predict who will experience prolonged suppression. Longer and heavier AAS exposure may increase concern for delayed recovery.
Dr. Marcus Vance, PharmD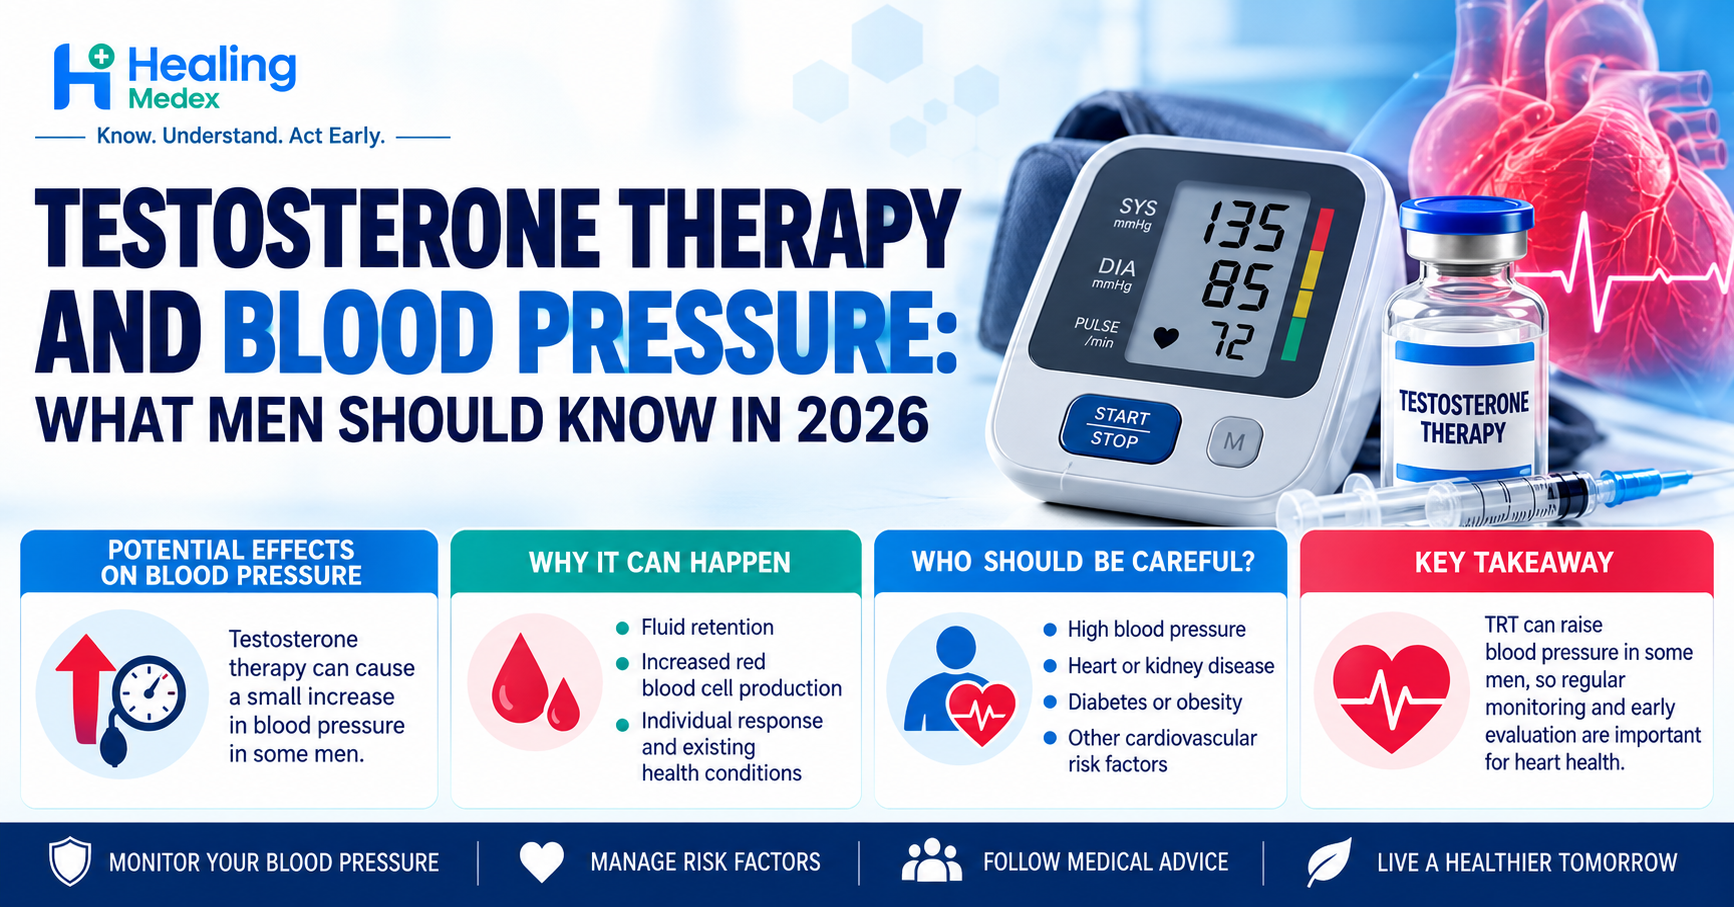
Anabolic Steriod
Testosterone Therapy and Blood Pressure: What Men Should Know in 2026
Testosterone replacement therapy (TRT) can improve symptoms in appropriately diagnosed men with testosterone deficiency, but treatment requires ongoing monitoring. One issue receiving increased attention in 2026 is blood pressure . Current evidence indicates that testosterone therapy can cause a small increase in blood pressure in some men , although the effect varies between individuals and testosterone formulations. This is particularly important for men who already have hypertension, diabetes, kidney disease, obesity, or cardiovascular disease. In 2025, the U.S. Food and Drug Administration (FDA) required testosterone products to carry updated warnings about increased blood pressure after ambulatory blood-pressure monitoring studies found increases across testosterone products. So, does testosterone therapy cause high blood pressure? And what should men using TRT monitor in 2026? Does Testosterone Therapy Raise Blood Pressure? It can. Testosterone does not cause the same blood-pressure response in every person, but clinical studies show that some testosterone formulations can produce measurable increases in systolic blood pressure. For example, a study involving men with hypogonadism using testosterone gel for 16 weeks found an average increase of approximately 1.9 mm Hg in 24-hour systolic blood pressure . The researchers also noted that the effect appeared more pronounced in some men who already had hypertension or diabetes. Another ambulatory blood-pressure study of transdermal testosterone reported an average increase of approximately 3.5 mm Hg in 24-hour systolic blood pressure among the evaluable participants. These averages may appear small, but even modest increases can matter when someone already has cardiovascular risk factors. What Changed With Testosterone Safety Warnings? A significant change occurred in February 2025 . Following review of postmarketing ambulatory blood-pressure studies, the FDA concluded that the completed studies confirmed an increase in blood pressure associated with testosterone products and required updated labeling across the drug class. Current testosterone prescribing information may therefore include warnings advising clinicians to: monitor blood pressure periodically; consider cardiovascular risk; pay particular attention to men who already have hypertension; and appropriately manage blood pressure during treatment. For example, updated prescribing information for testosterone gel states that testosterone can increase blood pressure and advises periodic BP measurement. Why Might Testosterone Affect Blood Pressure? Several factors could contribute. 1. Fluid and Sodium Retention Androgens can promote fluid retention in susceptible individuals. More retained fluid can increase circulating blood volume and potentially contribute to higher blood pressure. Fluid retention may be particularly important in people who already have heart, kidney, or liver disease . 2. Increased Red Blood Cell Production Testosterone stimulates production of red blood cells. As a result, TRT can increase: hemoglobin; hematocrit; and overall red blood cell mass. This is one reason hematocrit is routinely monitored during testosterone therapy. Excessive erythrocytosis can increase blood viscosity and may contribute to cardiovascular or thrombotic concerns, although blood pressure is influenced by many other factors as well. 3. Existing Cardiovascular Risk Men beginning testosterone therapy frequently have other conditions that influence blood pressure, such as: obesity; diabetes; sleep apnea; high cholesterol; kidney disease; physical inactivity; high sodium intake; or pre-existing hypertension. A rise in blood pressure during TRT therefore should not automatically be attributed to testosterone alone. The patient's complete cardiovascular health should be reviewed. Does Testosterone Therapy Increase Heart Attack or Stroke Risk? The answer is more nuanced than earlier warnings suggested. The large TRAVERSE trial included more than 5,200 men aged 45–80 with confirmed hypogonadism and either established cardiovascular disease or increased cardiovascular risk. Major cardiovascular events occurred in 7.0% of men receiving testosterone gel and 7.3% receiving placebo , meeting the trial's criteria for cardiovascular noninferiority. Based partly on these results, the FDA removed the previous boxed-warning language concerning an increased risk of major adverse cardiovascular outcomes from testosterone product labeling in 2025. At the same time, however, the FDA added or strengthened warnings about blood-pressure increases . These are two different issues. The TRAVERSE results should therefore not be interpreted as meaning that blood-pressure monitoring is unnecessary. Who Should Be Especially Careful? Blood-pressure monitoring is important for every man receiving TRT, but it deserves particular attention in men with: existing hypertension; previous heart attack or stroke; coronary artery disease; heart failure; kidney disease; diabetes; obesity; obstructive sleep apnea; high hematocrit; or multiple cardiovascular risk factors. Some current testosterone product labeling specifically states that treatment is not recommended in men with uncontrolled hypertension . Individual prescribing information should always be checked because warnings and risks can vary by formulation. What Blood Pressure Is Considered High in 2026? According to the 2025 AHA/ACC hypertension guideline , adult blood-pressure categories are: Blood Pressure Category Systolic Diastolic Normal Below 120 and below 80 Elevated 120–129 and below 80 Stage 1 hypertension 130–139 or 80–89 Stage 2 hypertension 140 or higher or 90 or higher The guideline generally identifies less than 130/80 mm Hg as the treatment goal for adults receiving treatment for hypertension, while individual circumstances still need to be considered. A single elevated reading does not necessarily establish hypertension. Clinicians usually look at repeated measurements and the patient's overall medical situation. Blood Pressure Monitoring Before Starting TRT Before testosterone therapy begins, a healthcare professional should review cardiovascular risk and obtain an accurate baseline blood-pressure measurement. Men should also be properly evaluated for testosterone deficiency. The Endocrine Society emphasizes that hypogonadism should be diagnosed based on compatible symptoms together with consistently low testosterone concentrations, generally confirmed with at least two early-morning testosterone measurements rather than symptoms alone. Baseline evaluation may include : blood pressure; testosterone levels; complete blood count and hematocrit; cardiovascular history; current medications; prostate assessment where appropriate; diabetes and cholesterol risk; and evaluation for conditions that could contribute to low testosterone. Blood Pressure Monitoring After Starting Testosterone Men receiving TRT should have their blood pressure checked periodically. Monitoring becomes especially useful: shortly after treatment begins; after the testosterone dose is changed; after changing testosterone formulations; if hypertension medications are changed; if significant weight or fluid retention develops; or if home blood-pressure measurements start trending upward. Home blood-pressure monitoring can provide additional information between medical visits. The 2025 hypertension guideline supports home BP monitoring as part of effective blood-pressure management. Use a validated upper-arm cuff rather than relying solely on cuffless smartwatches or similar devices for clinical decisions. What If Blood Pressure Goes Up During TRT? Do not automatically stop testosterone or change the dose without speaking to the prescribing clinician. The healthcare professional may investigate several possibilities, including: whether the testosterone dose is appropriate; whether testosterone levels are above the intended range; whether hematocrit has increased excessively; whether fluid retention is occurring; whether another medication is raising BP; whether sleep apnea is present or poorly controlled; diet and sodium intake; alcohol intake; body weight; and whether antihypertensive treatment needs adjustment. Depending on the findings, treatment might involve lifestyle measures, adjustment of blood-pressure medication, modification of testosterone therapy, or switching formulations. Can Men With High Blood Pressure Use Testosterone Therapy? Having hypertension does not automatically mean that every man is unable to receive testosterone. The important questions are whether testosterone therapy is medically indicated, whether the blood pressure is adequately controlled, and whether the patient can be appropriately monitored. Men with poorly controlled hypertension require additional caution because testosterone-related increases in BP could add to their existing cardiovascular risk. The decision should be individualized by the prescribing healthcare professional. Ways to Protect Cardiovascular Health During TRT Men receiving testosterone therapy can reduce overall cardiovascular risk by focusing on factors that are modifiable. These include: checking blood pressure regularly; taking prescribed hypertension medication consistently; reducing excess sodium; maintaining a healthy body weight; staying physically active; managing diabetes; controlling cholesterol; avoiding tobacco; limiting or avoiding excessive alcohol; treating sleep apnea when present; and attending scheduled TRT monitoring appointments. Current hypertension guidelines strongly recommend weight management, a heart-healthy dietary pattern, sodium reduction and regular physical activity for preventing and managing high blood pressure. When Does High Blood Pressure Require Urgent Care? Very high blood pressure deserves prompt attention. A blood pressure higher than 180/120 mm Hg is considered severe hypertension. If a reading above this level is accompanied by symptoms such as: chest pain; shortness of breath; weakness or numbness; difficulty speaking; sudden vision changes; or other symptoms suggesting acute organ damage, emergency medical assessment is required. Testosterone Therapy and Blood Pressure: Key Takeaway for 2026 Testosterone therapy can increase blood pressure, although the amount varies between individuals and formulations. The most important change men should understand in 2026 is that blood-pressure elevation is now recognized in U.S. testosterone labeling as a class-wide safety concern requiring monitoring . At the same time, evidence from the large TRAVERSE cardiovascular trial did not demonstrate a higher rate of major cardiovascular events with testosterone gel compared with placebo in appropriately selected men with hypogonadism and cardiovascular risk. Therefore, TRT should neither be viewed as universally dangerous for the heart nor treated as cardiovascularly risk-free. The practical approach is straightforward: Confirm that testosterone therapy is medically appropriate, control existing hypertension, monitor blood pressure and hematocrit, and regularly review cardiovascular risk with a healthcare professional. Frequently Asked Questions 1. Does TRT always raise blood pressure? No. Blood-pressure responses vary considerably. Some men experience little or no clinically important change, while others may develop a meaningful increase. 2. How much can testosterone raise blood pressure? The amount depends on the individual and formulation. Recent ambulatory BP studies have reported average systolic increases ranging from roughly 2 to several mm Hg with certain testosterone preparations. 3. Can I take blood-pressure medicine while using testosterone? Many men receiving TRT also take antihypertensive medication. Treatment needs to be individualized, and blood pressure should continue to be monitored by the prescribing clinician. 4. Should I stop TRT if my blood pressure becomes high? Do not change prescription testosterone therapy on your own. Contact your healthcare professional so the cause of the BP increase and the safest treatment strategy can be evaluated. 5. Is TRT safe for the heart? The TRAVERSE study found testosterone gel was noninferior to placebo for major adverse cardiovascular events in the population studied. However, testosterone still has important potential adverse effects and requires appropriate diagnosis, prescribing and monitoring
Dr. Marcus Vance, PharmD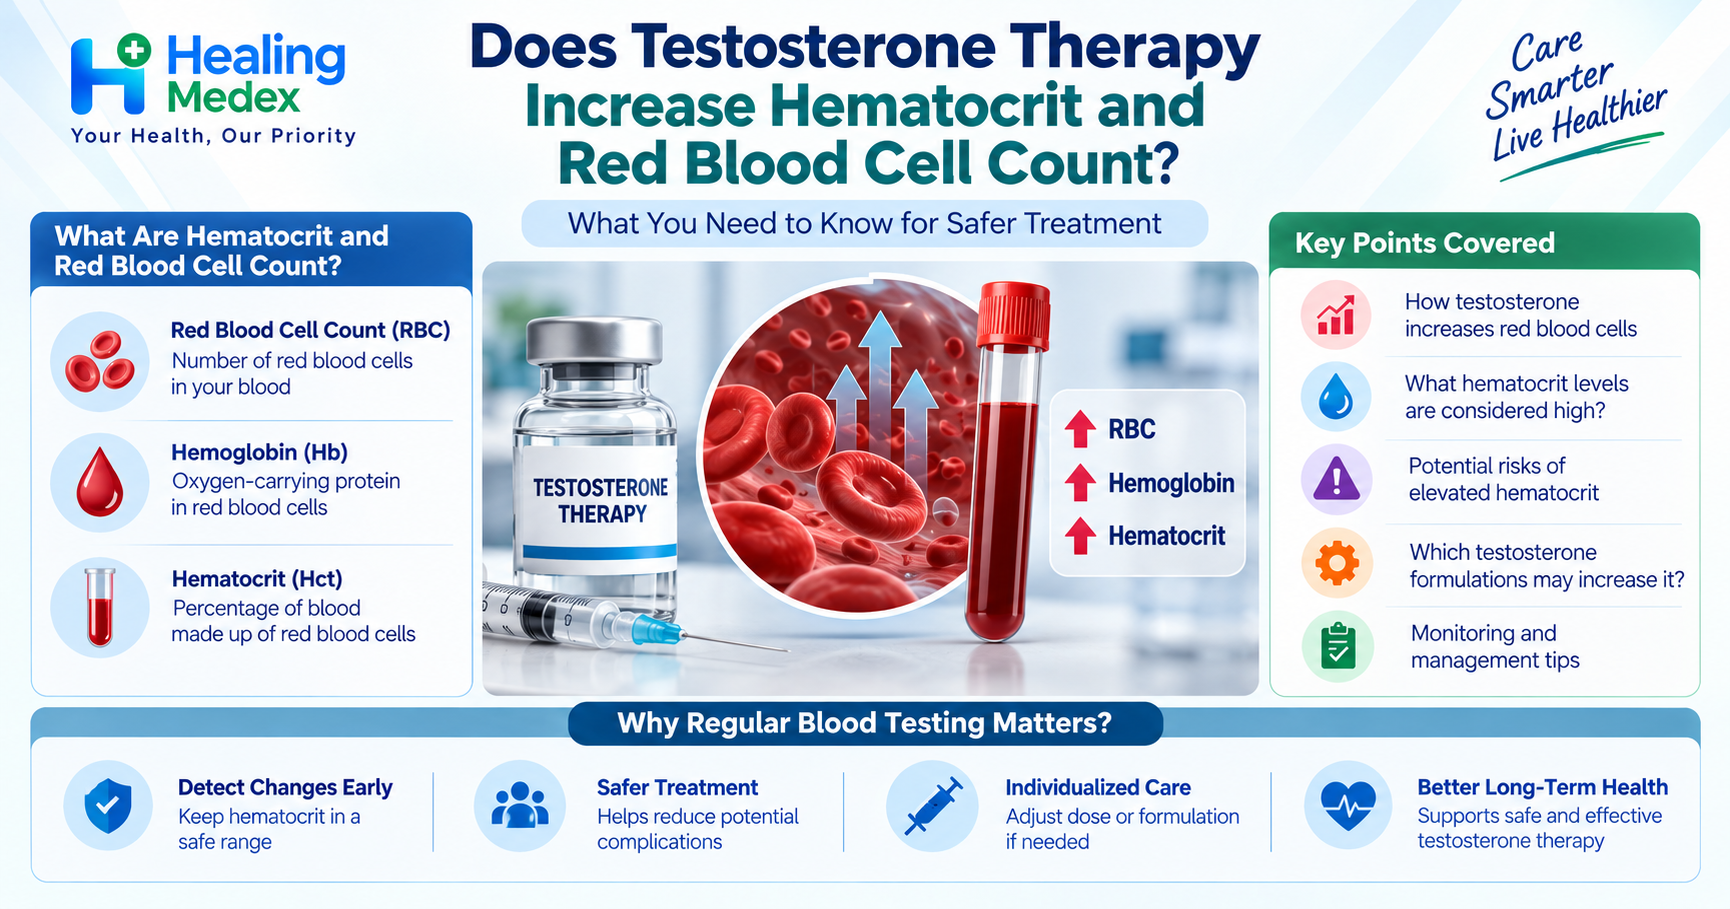
Anabolic Steriod
Does Testosterone Therapy Increase Hematocrit and Red Blood Cell Count?
Testosterone therapy is used to treat appropriately diagnosed testosterone deficiency, or hypogonadism. While treatment may improve symptoms in suitable patients, testosterone can also affect several laboratory values—including hemoglobin, hematocrit, and red blood cell count . One of the best-recognized effects of testosterone therapy is increased red blood cell production. In some patients, this rise is beneficial, particularly when low testosterone is associated with anemia. However, if hematocrit becomes too high, the condition is known as erythrocytosis , and treatment may need to be adjusted. So, does testosterone therapy increase hematocrit and red blood cells? Yes. It can—and regular blood testing is an important part of safe testosterone treatment. What Are Hematocrit and Red Blood Cell Count? Red blood cells, or RBCs, transport oxygen from the lungs to tissues throughout the body. Three commonly measured blood parameters are: Red blood cell count (RBC): the number of red blood cells in a given volume of blood. Hemoglobin (Hb): the oxygen-carrying protein contained within red blood cells. Hematocrit (Hct): the percentage of the blood volume made up of red blood cells. For example, a hematocrit of 45% means approximately 45% of the blood volume consists of red blood cells. These measurements are usually included in a complete blood count (CBC) . Does Testosterone Increase Red Blood Cell Production? Yes. Testosterone stimulates erythropoiesis , the process through which the body produces red blood cells. Consequently, hemoglobin and hematocrit commonly increase after testosterone therapy begins. The American Urological Association describes an increase in hemoglobin and hematocrit as the most frequent adverse laboratory effect associated with testosterone therapy. Levels often rise during approximately the first six months of treatment before tending to plateau. This effect does not automatically mean something is wrong. Testosterone can actually help correct anemia in some men with testosterone deficiency. Problems arise when red blood cell production becomes excessive. Why Does Testosterone Raise Hematocrit? Several biological mechanisms may contribute. 1. Testosterone stimulates erythropoietin Erythropoietin, commonly called EPO , is a hormone primarily produced by the kidneys that tells bone marrow to produce additional red blood cells. Testosterone may temporarily increase EPO activity and alter the body's normal relationship between EPO and hemoglobin. 2. Testosterone affects hepcidin Hepcidin helps regulate how iron is stored and made available within the body. Testosterone can suppress hepcidin, potentially making more iron available for the production of hemoglobin and new red blood cells. These mechanisms help explain why testosterone can progressively increase hemoglobin and hematocrit. What Is Testosterone-Induced Erythrocytosis? Erythrocytosis means that the amount of red blood cells in the circulation has become abnormally high. It is sometimes referred to as polycythemia, although testosterone-related secondary erythrocytosis is not the same condition as polycythemia vera , which is a bone-marrow disorder. According to the American Urological Association, hematocrit above approximately 52% is often used to define erythrocytosis, while a hematocrit of 54% or higher during testosterone treatment warrants clinical intervention . The exact laboratory reference range can vary according to the laboratory, sex, altitude, hydration status and other factors. Why Can Very High Hematocrit Be a Concern? When the proportion of red blood cells becomes excessive, blood viscosity may increase. This has raised concern about possible complications involving blood vessels, including: venous blood clots pulmonary embolism heart attack stroke However, the relationship between testosterone-induced erythrocytosis and cardiovascular or thrombotic events is complex. Reviews have found reasons for concern, while also noting that the precise level of risk and the best way to manage testosterone-induced erythrocytosis remain areas of ongoing research. This uncertainty is one reason clinicians focus on regular laboratory monitoring rather than waiting for symptoms to occur . What Hematocrit Level Is Too High During Testosterone Therapy? Clinical guidelines provide useful thresholds. The American Urological Association recommends checking hemoglobin and hematocrit before testosterone therapy begins. If hematocrit is already above 50% before treatment , clinicians should generally investigate why it is elevated and consider withholding testosterone until the cause is understood. During treatment: Hematocrit ≥54% generally requires intervention. Depending on the individual situation, intervention may include reducing the testosterone dose, temporarily stopping treatment, changing formulations or evaluating other causes of erythrocytosis. The Endocrine Society also recommends against beginning testosterone treatment in patients who already have an elevated hematocrit and emphasizes continued monitoring during therapy. Which Testosterone Formulations Are More Likely to Raise Hematocrit? The risk does not appear to be identical with every testosterone formulation. Injectable testosterone Intramuscular testosterone preparations—particularly formulations producing relatively high peaks in testosterone concentrations—have commonly been associated with larger increases in hematocrit. Examples can include: testosterone cypionate testosterone enanthate The AUA notes that clinical studies have generally found the greatest increases in hemoglobin and hematocrit with injectable testosterone compared with topical preparations. Testosterone gels and other transdermal preparations Transdermal testosterone generally produces steadier testosterone concentrations and may cause a smaller rise in hematocrit for some patients. A 2025 review similarly concluded that the route of testosterone administration can substantially influence hematocrit changes. However, any form of testosterone can potentially raise hematocrit , so monitoring remains necessary regardless of formulation. Who May Have a Higher Risk of Elevated Hematocrit? The likelihood of erythrocytosis can depend on more than testosterone alone. Factors clinicians may consider include: high testosterone doses or concentrations injectable testosterone preparations elevated hematocrit before starting treatment smoking obstructive sleep apnea chronic lung disease or chronic hypoxia living at high altitude dehydration increasing age other medications or medical conditions affecting red blood cell production Obstructive sleep apnea deserves particular attention because repeated reductions in oxygen during sleep can independently stimulate red blood cell production. Can High Hematocrit Cause Symptoms? Mild elevations may produce no noticeable symptoms , which is why routine blood tests are important. When hematocrit becomes substantially elevated, possible symptoms can include: headache dizziness unusual fatigue facial flushing blurred vision shortness of breath These symptoms are not specific to erythrocytosis and can have many other causes. Urgent medical assessment is appropriate for symptoms that could suggest a cardiovascular or thrombotic emergency, including sudden chest pain, sudden severe shortness of breath, coughing blood, one-sided leg swelling, sudden weakness, difficulty speaking or other symptoms suggestive of stroke. How Often Should Hematocrit Be Checked During Testosterone Therapy? A CBC should generally be obtained before testosterone treatment starts to establish baseline hemoglobin and hematocrit. Monitoring schedules can vary according to the patient, testosterone formulation, dose and clinician. Traditional Endocrine Society guidance has recommended checking hematocrit at baseline, again within the first several months of therapy and periodically thereafter. The Endocrine Society reaffirmed in July 2026 that appropriate diagnosis, screening and ongoing monitoring remain important for people receiving testosterone therapy. Patients should follow the testing schedule recommended by their treating clinician rather than relying on symptoms alone. What Happens If Hematocrit Becomes Too High? Treatment depends on the hematocrit level, testosterone concentration, formulation, symptoms and other medical conditions. A clinician may consider: Reducing the testosterone dose If testosterone concentrations are higher than necessary, lowering the dose can reduce stimulation of red blood cell production. Changing the dosing schedule Large fluctuations in testosterone concentration can sometimes contribute to erythrocytosis. A clinician may modify the dose or dosing interval depending on the preparation being used. Changing the testosterone formulation Someone who develops recurrent erythrocytosis while receiving injectable testosterone may sometimes be considered for a transdermal preparation. Temporarily stopping testosterone If hematocrit becomes significantly elevated, testosterone may be temporarily withheld until the level decreases. Looking for other causes Doctors may evaluate contributing factors such as: sleep apnea smoking chronic hypoxia lung disease dehydration high-altitude exposure If the elevated hematocrit cannot be explained by testosterone or common secondary causes, further hematologic evaluation may be necessary. Phlebotomy Therapeutic phlebotomy has traditionally been used in selected patients to reduce hematocrit by removing blood. However, newer reviews emphasize that evidence supporting routine phlebotomy specifically for testosterone-induced erythrocytosis is limited. Decisions about phlebotomy should therefore be individualized rather than performed without medical supervision. Should You Stop Testosterone if Your Hematocrit Is High? Do not change or stop prescribed testosterone solely on the basis of one laboratory result without discussing it with your healthcare provider unless urgent medical care is required. A high result may need to be repeated or interpreted alongside: hemoglobin red blood cell count testosterone concentration hydration status treatment dose timing of the testosterone measurement oxygen levels sleep apnea history smoking history other medical conditions and medications For hematocrit 54% or higher , major testosterone guidelines recommend clinical intervention rather than simply continuing the same treatment unchanged. Does a Higher Red Blood Cell Count Mean Testosterone Therapy Is Working Better? No. A larger increase in hematocrit does not mean testosterone treatment is more effective. The goal of medically supervised testosterone therapy is to treat confirmed testosterone deficiency while maintaining testosterone and other laboratory parameters within appropriate ranges—not to maximize testosterone, hemoglobin or hematocrit. Excessive dosing may increase adverse effects without providing additional therapeutic benefit. Can Testosterone Help Someone With Anemia? In appropriately selected patients, yes. Low testosterone can contribute to otherwise unexplained anemia in some men, and testosterone therapy can stimulate red blood cell production enough to improve hemoglobin levels. This beneficial effect and the risk of excessive erythrocytosis represent two sides of the same physiological process. The objective is therefore to maintain adequate red blood cell production without allowing hematocrit to become excessively elevated . Frequently Asked Questions 1.Does testosterone therapy increase hematocrit? Yes. Testosterone stimulates red blood cell formation, and increases in hemoglobin and hematocrit are well-recognized effects of treatment. 2.Is increased hematocrit common with testosterone injections? It can be. Injectable preparations have generally been associated with larger hematocrit increases than transdermal testosterone. 3.Is a hematocrit of 54% dangerous? A hematocrit of 54% or higher during testosterone therapy is an important clinical threshold requiring evaluation and intervention according to major guidelines . It does not mean every person at 54% will experience a complication, but it should not be ignored. 4.Can drinking water lower hematocrit? Dehydration can temporarily concentrate the blood and make hematocrit appear higher. Correcting dehydration may therefore change a mildly elevated result. However, hydration does not treat true testosterone-induced erythrocytosis. 5.Can testosterone therapy increase hemoglobin too? Yes. Because testosterone promotes red blood cell production, both hemoglobin and hematocrit usually rise together . 6.Can changing from injections to testosterone gel help? For some patients it may. Transdermal preparations generally produce smaller hematocrit increases than short-acting injectable testosterone, although individual responses vary. The Bottom Line Testosterone therapy can increase red blood cell count, hemoglobin and hematocrit. This is a normal physiological response to testosterone, but excessive red blood cell production can result in erythrocytosis. For people receiving testosterone therapy, safe treatment involves more than simply checking testosterone levels. Regular monitoring should include hemoglobin and hematocrit , particularly during the first several months after treatment begins or after dose changes. A high hematocrit does not automatically mean testosterone therapy must be permanently stopped. Depending on the situation, clinicians may adjust the dose, change the dosing schedule or formulation, investigate contributing conditions such as sleep apnea, or temporarily interrupt treatment.
Dr. Marcus Vance, PharmD
Anabolic Steriod
Testosterone Cypionate vs Testosterone Enanthate: What Is the Difference?
Testosterone cypionate and testosterone enanthate are two of the most widely used injectable forms of testosterone replacement therapy (TRT). Because both are long-acting testosterone esters, they have many similarities—and the differences between them are often smaller than people expect. Both medications ultimately deliver testosterone to the body. Their attached ester helps slow the release of testosterone after injection, allowing the medication to remain active longer than unmodified testosterone. So, is testosterone cypionate better than testosterone enanthate? Does one last longer? And are their side effects different? This article explains the key medical differences between testosterone cypionate vs testosterone enanthate , including how they work, how long they act, available formulations, potential side effects, and what patients should discuss with their healthcare provider. Important: Testosterone is a prescription medication and should be used only after appropriate medical evaluation. This article is for educational purposes and does not provide an individualized treatment or dosing plan. What Is Testosterone Replacement Therapy? Testosterone replacement therapy may be prescribed to men who have clinically confirmed testosterone deficiency caused by certain medical conditions. A diagnosis of hypogonadism should not be based on symptoms alone. The Endocrine Society recommends confirming testosterone deficiency in men who have compatible symptoms together with consistently low testosterone concentrations , typically using repeated morning testosterone measurements. Testosterone replacement can be administered through several formulations, including: Intramuscular injections Subcutaneous injections Gels Patches Nasal preparations Other approved testosterone formulations Testosterone cypionate and testosterone enanthate are among the commonly used injectable options. What Is Testosterone Cypionate? Testosterone cypionate is a long-acting ester of testosterone formulated in an oil-based injectable solution. After an intramuscular injection, the medication forms a depot from which testosterone cypionate is gradually absorbed. The ester is subsequently separated from the molecule, releasing active testosterone into the circulation. Current U.S. labeling describes testosterone cypionate as an oil-soluble testosterone ester intended for intramuscular administration. Its estimated intramuscular half-life is approximately eight days . Depending on the manufacturer, testosterone cypionate products may be supplied in concentrations such as 100 mg/mL or 200 mg/mL . What Is Testosterone Enanthate? Testosterone enanthate is another esterified, long-acting form of testosterone. Like cypionate, esterification slows testosterone release after injection. Standard testosterone enanthate injection products are oil-based and may be administered intramuscularly. For example, current U.S. testosterone enanthate labeling includes a 200 mg/mL intramuscular formulation containing testosterone enanthate in sesame oil. There is also an FDA-approved testosterone enanthate product called XYOSTED that uses a subcutaneous autoinjector , showing that the route of administration can depend on the specific product rather than simply the testosterone ester itself. Testosterone Cypionate vs Enanthate: Quick Comparison Feature Testosterone Cypionate Testosterone Enanthate Active hormone Testosterone Testosterone Ester Cypionate Enanthate Duration Long acting Long acting Common formulation Oil-based injection Oil-based injection Common route Intramuscular Intramuscular; some products are subcutaneous Typical concentration Often 100 or 200 mg/mL Commonly 200 mg/mL for IM products Release pattern Gradual Gradual Main medical purpose Testosterone replacement in appropriately diagnosed patients Testosterone replacement in appropriately diagnosed patients Side-effect profile Very similar Very similar Controlled medication in U.S. Schedule III Schedule III Both intramuscular testosterone cypionate and testosterone enanthate labels describe dosing intervals extending into the two-to-four-week range , although actual treatment schedules must be individualized according to the product, blood tests, clinical response, and prescriber instructions. 1. The Main Difference Is the Ester The primary chemical difference is the ester attached to the testosterone molecule. Testosterone cypionate contains a cypionate ester , while testosterone enanthate contains an enanthate ester . The ester itself is not responsible for testosterone's main androgenic effects. Instead, it changes characteristics such as how slowly the injected medication leaves the oil depot and becomes available. Once the ester is removed inside the body, both ultimately provide active testosterone. For most patients receiving medically supervised TRT, this means their overall physiological actions are highly similar. 2. Does Testosterone Cypionate Last Longer Than Enanthate? Testosterone cypionate and testosterone enanthate are both considered long-acting testosterone preparations. U.S. labeling for testosterone cypionate reports an intramuscular half-life of approximately eight days. Standard testosterone enanthate labeling similarly describes slow absorption from an intramuscular oil depot and states that the medication can be administered at extended intervals. Although pharmacokinetic differences between the two esters exist, they are generally more similar than different in routine clinical use . Individual testosterone levels can also vary considerably depending on: Dose Injection interval Route of administration Metabolism SHBG levels Age Body composition Timing of blood tests For this reason, treatment decisions should be guided by laboratory monitoring and symptoms rather than assuming one ester will automatically provide better or more stable testosterone levels. 3. Are Their Injection Schedules Different? Not necessarily. Current U.S. prescribing information for both traditional intramuscular testosterone cypionate and testosterone enanthate includes replacement-therapy dosing ranges administered at intervals of approximately two to four weeks . However, these label ranges should not be interpreted as a personal treatment schedule. A clinician may adjust treatment based on factors such as: Testosterone blood levels Clinical response Hematocrit Adverse effects Age Underlying cause of hypogonadism Specific testosterone product being used Patients should not independently increase doses, shorten injection intervals, or switch testosterone preparations. 4. Is One More Effective for Low Testosterone? Both cypionate and enanthate supply testosterone, so their therapeutic goal is essentially the same: restoring testosterone exposure in an appropriately diagnosed patient. When testosterone concentrations are maintained within an appropriate physiological range, either formulation may help improve symptoms related to genuine testosterone deficiency. Potential improvements in appropriately selected patients may include changes in: Sexual function Libido Energy Lean body mass Bone health Certain symptoms associated with testosterone deficiency There is no simple medical rule stating that testosterone cypionate is universally more effective than testosterone enanthate or vice versa. Treatment response depends substantially more on appropriate diagnosis, dose selection, monitoring, and individual physiology . 5. Do They Produce Different Testosterone Levels? Both preparations can produce rises and falls in testosterone after an injection. Injectable testosterone is absorbed gradually from the injection site, but serum concentrations can still fluctuate between doses. How significant those fluctuations become depends on the formulation and treatment schedule. A patient experiencing symptoms before the next scheduled injection should discuss them with their clinician rather than changing the schedule without medical supervision. Blood testing can help determine whether testosterone exposure is appropriate. 6. Do Cypionate and Enanthate Have Different Side Effects? Their side-effect profiles overlap substantially because the active hormone produced by both formulations is testosterone. Potential effects associated with testosterone therapy can include: Acne or oily skin Increased red blood cell production Increased hematocrit Fluid retention Gynecomastia Changes in libido Changes in cholesterol Injection-site discomfort Suppression of natural testosterone production Reduced sperm production Potential worsening of sleep apnea in susceptible individuals Testosterone products have also been associated with venous thromboembolic events, including deep-vein thrombosis and pulmonary embolism. The exact risk profile varies by patient and formulation. 7. Can Testosterone Raise Hematocrit? Yes. Testosterone stimulates red blood cell production. In some people, this can cause hematocrit to rise excessively—a condition sometimes described as testosterone-associated erythrocytosis or polycythemia. For this reason, hematocrit is an important laboratory value during testosterone therapy. Current testosterone labeling recommends checking hematocrit before treatment and monitoring it during therapy. Very high hematocrit may require adjustment or interruption of treatment by the prescribing clinician. 8. Can Testosterone Affect Blood Pressure? Testosterone products can increase blood pressure in some patients. Current testosterone prescribing information advises periodic blood-pressure monitoring, particularly in patients who already have hypertension. People with cardiovascular risk factors should discuss them with their healthcare provider before beginning testosterone replacement. 9. Can Testosterone Cypionate or Enanthate Affect Fertility? Yes. An important but sometimes overlooked effect of testosterone replacement therapy is suppression of the body's reproductive hormone signaling. External testosterone can reduce secretion of luteinizing hormone and follicle-stimulating hormone, which may reduce testosterone production inside the testes and impair sperm production. Testosterone therapy can therefore cause: Reduced sperm count Oligospermia Azoospermia Reduced fertility Current testosterone enanthate labeling specifically warns that exogenous androgens may negatively affect spermatogenesis. The Endocrine Society recommends against beginning testosterone therapy in men who are planning fertility in the near future. Anyone hoping to conceive should tell their clinician before starting TRT. 10. What Monitoring Is Needed During TRT? Testosterone replacement should not be treated as a medication that can simply be started and forgotten. Monitoring may include evaluation of: Testosterone Levels Blood testing helps determine whether testosterone concentrations are in an appropriate therapeutic range. Hematocrit and Hemoglobin These tests help identify excessive red blood cell production. Blood Pressure Testosterone can increase blood pressure in some individuals. Prostate Health Depending on age and individual risk factors, prostate-related evaluation may be appropriate. Treatment Response Clinicians should assess whether symptoms are actually improving. Adverse Effects Acne, edema, urinary symptoms, sleep apnea symptoms, fertility concerns, and other adverse effects should be reviewed. The Endocrine Society recommends evaluating patients after starting therapy to determine clinical response, adverse effects, and adherence. Testosterone Cypionate vs Enanthate: Which Is Better? There is no universally superior option. For medically supervised testosterone replacement, cypionate and enanthate are closely related medications that ultimately provide the same active hormone. The most suitable preparation may depend on: Product availability Route of administration Formulation ingredients Cost Insurance coverage Injection preferences Previous response Adverse effects Clinician experience Local regulatory approval Someone who responds well to one formulation may have little reason to switch simply because another ester is promoted as being “better.” Is Testosterone Enanthate Available as a Subcutaneous Injection? Yes, depending on the specific product. Traditional testosterone enanthate preparations are administered intramuscularly. However, XYOSTED is an FDA-approved testosterone enanthate autoinjector designed for subcutaneous administration . It is available in 50 mg, 75 mg, and 100 mg single-dose autoinjectors in the United States. Patients should therefore follow the instructions for their exact medication rather than assuming all testosterone enanthate products are injected the same way. What About Testosterone Use for Bodybuilding? Prescription testosterone is intended for specific medical conditions, not unsupervised bodybuilding or performance enhancement. Taking testosterone at higher-than-prescribed doses or combining it with other anabolic-androgenic steroids may substantially increase health risks. Reported complications associated with anabolic-androgenic steroid misuse include cardiovascular problems, fertility impairment, abnormal cholesterol, testicular atrophy, psychiatric effects, and other serious adverse outcomes. Both testosterone cypionate and testosterone enanthate are Schedule III controlled substances in the United States . Frequently Asked Questions 1. Is testosterone cypionate stronger than testosterone enanthate? Not in a meaningful general sense. Both are esterified forms of testosterone that release active testosterone after administration. Treatment effectiveness depends more on achieving appropriate testosterone exposure than simply choosing one ester over another. 2. Which lasts longer: testosterone cypionate or enanthate? Both are long-acting injectable testosterone esters. Testosterone cypionate has an approximately eight-day intramuscular half-life according to prescribing information, while testosterone enanthate is also slowly absorbed from its oil depot. Their practical duration of action is broadly similar. 3. Can you switch from testosterone enanthate to cypionate? A healthcare professional can switch testosterone formulations when appropriate, but patients should not perform a milligram-for-milligram substitution themselves. Concentration, route, dosing schedule, blood levels, and the characteristics of the specific product need to be considered. 4. Do both forms suppress natural testosterone? Yes. External testosterone can suppress the hypothalamic-pituitary-gonadal axis, reducing the body's own testosterone and sperm production. 5. Can testosterone injections cause infertility? They can significantly reduce sperm production in some men. Testosterone therapy is therefore generally inappropriate for men actively trying to conceive unless their reproductive specialist recommends another approach. 6. Can testosterone increase red blood cells? Yes. Increased hematocrit is a recognized effect of testosterone treatment and requires monitoring. 7. Is testosterone cypionate safer than testosterone enanthate? Neither is inherently risk-free. Because both ultimately deliver testosterone, many of their important risks overlap. Safety depends on appropriate patient selection, dosing, monitoring, underlying health conditions, and correct use. The Bottom Line Testosterone cypionate and testosterone enanthate are much more alike than they are different. Both are long-acting testosterone esters designed to provide sustained testosterone exposure. Their main difference is the chemical ester attached to testosterone, along with product-specific differences such as formulation, concentration, carrier oil, injection route, and availability. For patients with confirmed testosterone deficiency, either formulation may be appropriate when prescribed and monitored by a qualified healthcare professional. Choosing between them should not be based on bodybuilding claims or assumptions that one ester is automatically stronger. The more important factors are obtaining an accurate diagnosis, selecting an appropriate formulation, monitoring testosterone and hematocrit, evaluating blood pressure and other risk factors, and adjusting treatment according to clinical response. Anyone considering testosterone therapy—especially someone who wants to preserve fertility or has cardiovascular, prostate, sleep-apnea, or blood-pressure concerns—should discuss those issues with a healthcare professional before treatment.
Dr. Marcus Vance, PharmD
Erectile Dysfunction
Erectile Dysfunction Under 40: 10 Causes Younger Men Often Overlook
Erectile dysfunction (ED) is often associated with older age, but erection problems can also affect men in their 20s and 30s. Being young does not automatically mean that erectile dysfunction is “just psychological.” ED means having persistent or recurring difficulty getting an erection or keeping one firm enough for satisfactory sexual activity. Psychological factors such as stress and performance anxiety are important in younger men, but physical causes—including diabetes, cardiovascular risk factors, hormonal disorders, medications and substance use—also need to be considered. For men under 40, erectile dysfunction can sometimes be an early clue that something else is affecting physical or emotional health. Here are 10 commonly overlooked causes of erectile dysfunction in younger men . 1. Performance Anxiety One of the most common problems in younger men is worrying about whether they will be able to get or maintain an erection. A single episode of difficulty can sometimes start a cycle: Erection difficulty → worry about it happening again → increased anxiety → greater difficulty getting an erection. Stress activates the body's sympathetic nervous system—the “fight or flight” response—which can interfere with the relaxation and blood-flow changes required for an erection. Performance anxiety may be especially likely when erections are normal during sleep or masturbation but become difficult during partnered sexual activity. However, this pattern alone cannot confirm the cause. Anxiety, depression, stress, low self-esteem and negative body image are all recognized psychological factors that may contribute to ED. What to consider: Persistent anxiety, relationship stress or fear surrounding sexual performance may be worth discussing with a healthcare professional or qualified therapist. 2. Chronic Stress and Mental Health Problems It is not only sexual performance anxiety that can affect erections. Work pressure, financial stress, relationship problems, depression and generalized anxiety may reduce sexual arousal and interfere with erectile function. Chronic stress may also affect sleep, alcohol consumption, exercise and overall cardiovascular health—all factors that can influence sexual function. Depression may reduce sexual interest, while some medicines used to treat depression can themselves contribute to sexual side effects. Key point: Erectile dysfunction can have both physical and psychological components at the same time. It does not always have a single cause. 3. Medicines You Would Not Expect to Affect Erections Younger men sometimes overlook their medications when trying to understand why ED has developed. Medicines associated with erectile problems can include certain: Antidepressants Blood pressure medicines Diuretics Antihistamines Sedatives Opioid pain medicines Hormonal medicines Some other prescription and over-the-counter drugs NIDDK lists medications among the recognized causes of erectile dysfunction. If erection problems began after starting a medicine or changing its dose, tell your healthcare provider. Important: Do not stop a prescribed medicine suddenly because of sexual side effects. A clinician may be able to adjust the dose, change the medicine or investigate another cause. 4. Prediabetes or Diabetes Diabetes is not only a condition affecting older adults. Type 2 diabetes can develop in younger men, particularly when other risk factors such as excess body weight, inactivity or family history are present. Persistently elevated blood glucose can damage both the blood vessels and nerves involved in erections. Interestingly, sexual problems can occasionally be one of the health changes that encourage someone to undergo metabolic testing. Men with diabetes may also develop erectile dysfunction earlier than men without diabetes. Possible accompanying signs of diabetes include: Increased thirst Frequent urination Unexplained fatigue Blurred vision Slow-healing wounds However, diabetes can also exist for some time without obvious symptoms. What may be checked: A healthcare professional may consider fasting glucose or HbA1c depending on your history and risk factors. 5. High Cholesterol, High Blood Pressure and Early Blood-Vessel Problems An erection depends heavily on healthy blood flow. Conditions affecting the lining of blood vessels—known as the endothelium—can therefore interfere with erectile function. High cholesterol, hypertension, smoking, diabetes and obesity can contribute to vascular dysfunction even in younger adults. This is particularly important because erectile dysfunction is recognized by major urology guidelines as a potential risk marker for cardiovascular disease . Research examining young men with ED has also found evidence that metabolic and cardiovascular risk factors should not automatically be dismissed simply because someone is under 40. This does not mean that a young man with ED necessarily has heart disease. It means persistent or unexplained ED can provide a reason to review cardiovascular risk factors rather than assuming the problem is purely psychological. 6. Excess Weight and Physical Inactivity Being overweight does not automatically cause erectile dysfunction, but excess body fat and inactivity may increase several conditions associated with ED. These include: Insulin resistance Type 2 diabetes High blood pressure Abnormal cholesterol Reduced cardiovascular fitness Hormonal abnormalities Regular physical activity supports cardiovascular function and blood circulation throughout the body. NIDDK recommends lifestyle measures such as physical activity, maintaining a healthy body weight, stopping smoking and following a healthy eating pattern as part of preventing or improving erectile problems. Improving overall metabolic health may therefore benefit both long-term cardiovascular health and sexual function. 7. Smoking, Heavy Alcohol Use and Recreational Drugs Smoking can damage blood vessels and interfere with healthy circulation. Because erections depend on adequate arterial blood flow, vascular damage associated with smoking may contribute to erectile dysfunction. Excessive alcohol can also interfere with sexual arousal and the nervous-system signals involved in erections. Recreational and illicit drugs may affect sexual function in different ways depending on the substance. NIDDK identifies smoking, excessive alcohol consumption and recreational or illicit drug use among lifestyle factors associated with ED. Younger men may overlook these factors because they otherwise feel physically healthy. Occasional erection difficulty after drinking heavily is different from persistent ED , but repeated problems warrant attention. 8. Low Testosterone or Other Hormonal Problems Testosterone is important for sexual desire and normal sexual function, but ED does not automatically mean testosterone is low. In fact, many younger men presenting with erectile dysfunction have normal testosterone levels. One large study of men under 40 with ED found that the majority had a normal hormonal environment. However, hormonal conditions can contribute in some men. Possible problems include: Low testosterone Thyroid disorders Abnormal prolactin levels Pituitary disorders Other endocrine conditions Low testosterone may be more likely when ED occurs alongside symptoms such as: Reduced sex drive Fatigue Loss of muscle mass Reduced morning erections Fertility problems Hormone testing should be guided by a healthcare professional rather than relying on symptoms alone. 9. Anabolic Steroid or Non-Medical Testosterone Use This cause may be especially easy to overlook in younger men who use bodybuilding or performance-enhancing drugs. Taking anabolic-androgenic steroids can suppress the body's own hypothalamic-pituitary-gonadal hormonal system. While sexual function may appear normal—or sometimes heightened—during androgen use, stopping anabolic steroids can result in suppressed natural testosterone production. Possible symptoms after discontinuation can include: Low libido Erectile dysfunction Fatigue Depressed mood Reduced testicular function Fertility problems Research has documented prolonged hormonal suppression and impaired sexual function in some former anabolic-steroid users. Recovery varies significantly between individuals. Anyone experiencing sexual or hormonal symptoms after anabolic steroid use should discuss the history openly with an endocrinologist, urologist or other qualified healthcare professional rather than attempting unsupervised hormonal treatment. 10. Pelvic, Nerve or Penile Problems Occasionally, erectile dysfunction in younger men has a structural or neurological cause. Examples include: Pelvic or perineal injury Spinal cord or nerve injury Previous pelvic surgery Peyronie's disease Significant penile trauma Vascular injury Long periods of intense cycling have also been investigated because pressure from a bicycle saddle can compress nerves and blood vessels in the perineal region. Older clinical research in young men with organic ED identified perineal trauma and vascular abnormalities among possible causes. Peyronie's disease involves scar tissue within the penis that may cause curvature, discomfort and sometimes erectile problems. Seek medical assessment if ED is accompanied by penile pain, a new curvature, numbness, significant pelvic trauma or neurological symptoms. Is Erectile Dysfunction Under 40 Usually Psychological? Not necessarily. Psychological causes are important in younger men, but assuming all ED under 40 results from anxiety can cause physical conditions to be overlooked. Research has shown that younger men may have psychological, organic or mixed causes of erectile dysfunction. A young man might, for example, have mild vascular dysfunction that creates occasional erection difficulty. Worrying about the problem can then create performance anxiety, making the original physical problem worse. Therefore, psychological and physical ED are not always separate conditions. When Should a Young Man See a Doctor About ED? One unsuccessful sexual experience is not necessarily erectile dysfunction. Temporary erection difficulties can happen because of: Stress Fatigue Alcohol Relationship problems Anxiety Temporary illness However, medical evaluation is reasonable when erection problems: Continue for several weeks or months Happen frequently Are becoming progressively worse Occur during both partnered sex and masturbation Are associated with reduced libido Begin after starting a medication Follow anabolic steroid use Occur alongside diabetes or cardiovascular risk factors Are associated with penile curvature or pain ED can sometimes provide an opportunity to identify another health condition earlier. Both American and European urology guidance recognize the relationship between ED and cardiovascular risk. How Is Erectile Dysfunction in Younger Men Evaluated? A doctor will usually begin with a medical, sexual and mental-health history. Evaluation may include: Blood pressure Weight and waist assessment Cardiovascular risk factors Medication and supplement review Smoking, alcohol and recreational drug history Sexual history Mental health and relationship factors Physical examination Depending on the individual, laboratory tests may include blood glucose, cholesterol and testosterone. Additional hormone or specialist testing may be recommended when symptoms suggest a particular problem. Specialized testing such as penile Doppler ultrasound is usually reserved for selected patients rather than being necessary for every case. Can Erectile Dysfunction Under 40 Be Treated? In many cases, yes. Treatment depends on the underlying cause and may include: Managing diabetes, cholesterol or blood pressure Stopping smoking Reducing excessive alcohol Increasing physical activity Weight management Addressing anxiety or depression Counseling or sex therapy Reviewing medicines contributing to ED Treating confirmed hormonal disorders Prescription ED medications when appropriate PDE5 inhibitors such as sildenafil or tadalafil increase blood flow to the penis and are commonly used treatments for ED, but they do not identify or correct every underlying cause. A medical assessment is particularly valuable when ED develops unexpectedly in a younger person. Never use prescription ED medication obtained from an unreliable source or combine ED medicines with nitrate medicines without medical advice because potentially serious interactions can occur. Frequently Asked Questions Is erectile dysfunction normal at 25 or 30? Occasional difficulty getting an erection can happen at any age. Frequent or persistent ED at 25 or 30 should not simply be considered normal and is worth discussing with a healthcare professional. Can anxiety cause ED even if testosterone is normal? Yes. Anxiety, stress and performance pressure can interfere with the nervous-system and arousal processes required for an erection even when hormone levels are normal. Can a young man have ED because of poor blood circulation? Yes. Diabetes, smoking, hypertension, abnormal cholesterol, obesity and other vascular factors can affect blood circulation at a younger age. Does ED under 40 mean heart disease? No. ED has many possible causes, and having ED does not mean someone has cardiovascular disease. However, persistent ED can be a cardiovascular risk marker , which is why reviewing blood pressure, glucose, cholesterol and other risk factors may be appropriate. Can anabolic steroids cause erectile dysfunction? They can contribute, particularly after discontinuation. Anabolic steroids may suppress natural hormone production, and some former users develop low libido, hormonal symptoms or ED during recovery. Final Takeaway Erectile dysfunction under 40 should not automatically be dismissed as a psychological problem. Performance anxiety and stress are common contributors, but younger men can also experience ED because of medications, diabetes, vascular problems, smoking, excess weight, hormonal disorders, anabolic steroid use or neurological and structural conditions. Persistent ED can sometimes be the first reason an otherwise healthy young man discovers an underlying metabolic or cardiovascular risk factor. Rather than simply treating the erection problem, identifying why it is happening can lead to more appropriate treatment and better long-term health.
Dr. Marcus Vance, PharmD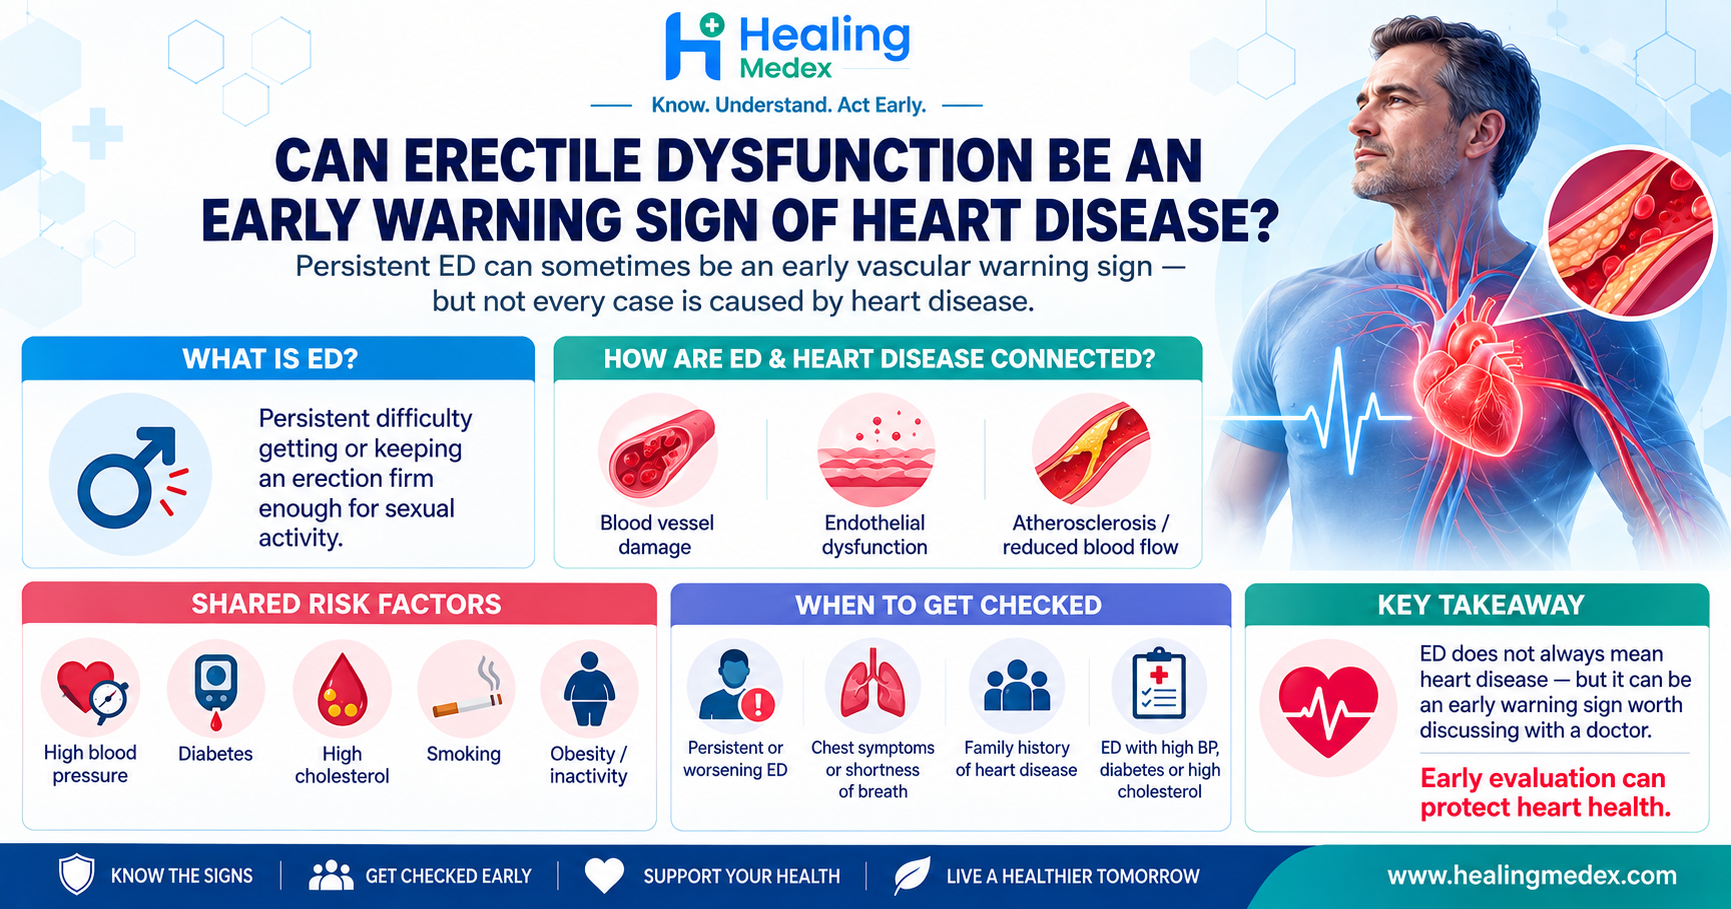
Erectile Dysfunction
Can Erectile Dysfunction Be an Early Warning Sign of Heart Disease?
Erectile dysfunction (ED) is often thought of only as a sexual health problem. However, persistent difficulty getting or maintaining an erection can sometimes provide an important clue about a man's overall cardiovascular health. The reason is simple: healthy erections depend on healthy blood vessels and good blood flow . Many of the same conditions that damage the arteries supplying the heart can also reduce blood flow to the penis. In some men, erectile dysfunction may therefore appear before more obvious symptoms of cardiovascular disease , such as chest pain. Current cardiovascular and sexual-medicine guidance recognizes ED as an important cardiovascular risk marker. The Princeton IV Consensus describes erectile dysfunction as a cardiovascular risk-enhancing factor, while European cardiovascular guidance notes that ED may precede coronary artery disease and other vascular disease by several years. So, can erectile dysfunction be an early warning sign of heart disease? Yes, it can—but not every case of ED is caused by heart disease. Understanding the connection can help men recognize when further medical evaluation may be worthwhile. What Is Erectile Dysfunction? Erectile dysfunction is the persistent difficulty getting or maintaining an erection firm enough for satisfactory sexual activity. An occasional erection problem is common and may happen because of: Stress Fatigue Anxiety Relationship problems Excess alcohol Poor sleep Temporary illness However, when erection problems happen repeatedly or persist for several months, an underlying medical condition may sometimes be involved. Possible physical causes include diabetes, high blood pressure, high cholesterol, obesity, hormonal disorders, neurological conditions, medication side effects and cardiovascular disease. How Are Erectile Dysfunction and Heart Disease Connected? The penis and heart may seem unrelated, but both depend heavily on healthy arteries. During sexual arousal, blood vessels supplying the penis must relax and widen so that enough blood can enter the erectile tissue. When blood vessels are damaged or narrowed, this process becomes more difficult. Two important mechanisms link ED and cardiovascular disease: 1. Endothelial Dysfunction The endothelium is the thin layer of cells lining the inside of blood vessels. A healthy endothelium helps arteries expand by producing substances such as nitric oxide. Conditions including: High blood pressure Diabetes Smoking High cholesterol Obesity can damage the endothelium. When endothelial function declines, arteries may not widen properly. Reduced blood flow can affect both the penis and the heart. Mayo Clinic notes that endothelial dysfunction can reduce blood supply to both organs and may eventually contribute to atherosclerosis. 2. Atherosclerosis Atherosclerosis occurs when cholesterol, fats and other substances accumulate inside artery walls and form plaque. As plaque develops, arteries can become narrower and less flexible. Reduced blood flow through penile arteries may contribute to erectile difficulties, while narrowing of coronary arteries can eventually contribute to angina, heart attack and other cardiovascular problems. Why Might ED Appear Before Heart Symptoms? One explanation is often called the artery-size hypothesis . The arteries supplying the penis are smaller than many major arteries supplying the heart. Because they are smaller, changes affecting blood-vessel function may sometimes interfere with penile blood flow before they produce obvious symptoms from larger coronary arteries. Recent Mayo Clinic guidance notes that penile arteries are approximately 1–2 mm wide and that ED can sometimes occur before clinically obvious coronary disease. That does not mean every man with ED has blocked coronary arteries. But persistent ED—particularly without an obvious psychological, hormonal or medication-related explanation—can be a reason to evaluate cardiovascular risk. How Long Before Heart Disease Can ED Appear? Research and cardiovascular guidelines suggest that erectile dysfunction can sometimes occur approximately 2–5 years before clinically apparent cardiovascular disease , with an average interval of around three years reported in European cardiovascular guidance. Mayo Clinic has similarly highlighted that ED may occur several years before cardiovascular events become apparent. This potential time gap is important because it can create an opportunity to identify and address cardiovascular risk factors earlier. Does Having Erectile Dysfunction Mean You Have Heart Disease? No. Erectile dysfunction has many possible causes, and cardiovascular disease is only one of them. Other causes include: Psychological factors Stress, anxiety, depression, performance anxiety and relationship difficulties can interfere with sexual arousal. Low testosterone or other hormonal disorders Hormonal problems may affect libido and sexual function. Diabetes Long-term high blood sugar can damage both nerves and blood vessels involved in erections. Neurological conditions Conditions affecting nerve signaling between the brain, spinal cord and penis may cause ED. Medicines Some medicines used for high blood pressure, depression and other health conditions can contribute to erection difficulties. Alcohol and recreational drugs Heavy alcohol consumption and certain drugs can interfere with erectile function. Sleep disorders Poor sleep and sleep apnea may contribute to hormonal and cardiovascular abnormalities associated with ED. Therefore, erectile dysfunction should be considered a possible health signal rather than a diagnosis of heart disease . Cardiovascular Risk Factors Shared by ED and Heart Disease ED and cardiovascular disease share many of the same risk factors. These include: High blood pressure High LDL cholesterol Diabetes Smoking Obesity Physical inactivity Metabolic syndrome Poor diet Increasing age European cardiovascular guidelines specifically identify hypertension, high cholesterol, insulin resistance or diabetes, smoking, obesity, metabolic syndrome and sedentary lifestyle among shared risk factors for ED and cardiovascular disease. The more cardiovascular risk factors a person has, the more important it may be to investigate persistent ED rather than treating the erection problem alone. When Should ED Raise More Concern About Heart Health? A cardiovascular assessment may be particularly important when ED: Appears suddenly without an obvious explanation Persists or gradually becomes worse Occurs together with high blood pressure Occurs in someone with diabetes Is accompanied by high cholesterol Develops in a smoker Occurs in someone who is overweight or physically inactive Occurs in a man with a strong family history of premature cardiovascular disease Develops despite otherwise normal sexual desire ED in younger men should not automatically be assumed to be psychological. Princeton IV guidance emphasizes considering ED as a cardiovascular risk marker, including in men who may otherwise appear healthy. What Heart Tests Might Be Recommended for Someone With ED? Not everyone with erectile dysfunction requires extensive cardiac testing. Evaluation generally begins with medical history, physical examination and cardiovascular risk assessment. A healthcare professional may consider checking: Blood pressure High blood pressure damages arteries over time and may contribute to both ED and cardiovascular disease. Cholesterol A lipid profile may identify elevated LDL cholesterol, triglycerides or other abnormalities associated with atherosclerosis. Blood glucose or HbA1c Previously undiagnosed diabetes or prediabetes may contribute to ED. Weight and waist circumference Excess body fat, particularly abdominal obesity, is associated with metabolic and cardiovascular risk. Smoking history Smoking damages blood vessels and substantially increases cardiovascular risk. Family history Premature heart disease in close relatives may increase cardiovascular risk. Depending on age, symptoms and overall risk, additional cardiovascular testing may sometimes be considered. The Princeton IV Consensus recommends considering coronary artery calcium (CAC) scoring in selected men with ED whose calculated cardiovascular risk is borderline or intermediate when additional information would help guide prevention decisions. A CAC scan is not necessary for every man with erectile dysfunction, so the decision should be individualized with a healthcare professional. Can Improving Heart Health Improve Erectile Function? In some men, yes. Measures that improve cardiovascular health may also improve blood-vessel function and erections. Helpful strategies include: Exercise Regularly Regular physical activity improves cardiovascular fitness, circulation, blood pressure, metabolic health and weight control. Stop Smoking Smoking damages the blood-vessel lining and accelerates atherosclerosis. Stopping smoking can benefit both cardiovascular and sexual health. Maintain a Healthy Weight Weight reduction may improve blood pressure, blood sugar control and vascular function. Control Blood Pressure Untreated hypertension can damage blood vessels. If ED develops after starting a blood-pressure medicine, talk to your doctor rather than stopping the medication yourself because some antihypertensive medicines are more likely than others to affect sexual function. Manage Cholesterol Reducing elevated cholesterol helps decrease the progression of atherosclerotic cardiovascular disease. Control Diabetes Maintaining appropriate blood glucose levels helps protect both blood vessels and nerves involved in erections. Eat a Heart-Healthy Diet A diet emphasizing vegetables, fruits, whole grains, legumes, nuts, fish and minimally processed foods can support cardiovascular health. European cardiovascular guidance notes that exercise, improved nutrition, weight control and smoking cessation may improve sexual function while also reducing cardiovascular risk. Can You Take ED Medicines If You Have Heart Disease? Many men with stable cardiovascular disease may be able to use PDE5 inhibitors such as: Sildenafil Tadalafil Vardenafil Avanafil However, cardiovascular status and current medications should be reviewed first. Important: PDE5 inhibitors and nitrates must not be combined. Nitrate medicines such as nitroglycerin/glyceryl trinitrate and isosorbide are commonly used for angina. Taking sildenafil or similar ED medicines together with nitrates can cause a potentially dangerous fall in blood pressure. Men with significant or unstable cardiovascular disease should therefore discuss both sexual activity and ED treatment with a healthcare professional before using these medicines. When Should You Seek Urgent Medical Attention? Erectile dysfunction itself is generally not a medical emergency. However, seek urgent medical help if you experience symptoms that may indicate a heart problem, including: Chest pain or pressure Severe shortness of breath Pain spreading to the arm, shoulder, jaw or back Fainting Sudden severe dizziness New or severe palpitations Unexplained sweating associated with chest discomfort Do not ignore these symptoms because they occur during sexual activity. Anyone who has taken an ED medicine such as sildenafil or tadalafil should also tell emergency healthcare professionals, particularly if treatment with nitrate medicines might otherwise be considered. Should Every Man With ED Get His Heart Checked? Not every occasional erection problem requires cardiac testing. But persistent or unexplained erectile dysfunction deserves medical evaluation , particularly when cardiovascular risk factors are present. A healthcare professional can evaluate both sexual health and cardiovascular risk rather than simply treating the symptom. This is especially useful because conditions such as: High blood pressure High cholesterol Prediabetes Diabetes may exist without obvious symptoms. Finding these conditions early can provide an opportunity to reduce future cardiovascular risk. The Bottom Line Erectile dysfunction can sometimes be an early warning sign of cardiovascular disease. ED and heart disease share many of the same underlying mechanisms, particularly blood-vessel dysfunction and atherosclerosis. Because penile arteries are relatively small, vascular problems may sometimes affect erectile function before obvious cardiac symptoms develop. Research and cardiovascular guidelines indicate that ED can precede clinically apparent cardiovascular disease by several years in some men. However, erectile dysfunction does not automatically mean that you have heart disease . Psychological factors, hormonal disorders, diabetes, medications, neurological problems and other conditions can also cause ED. If erectile dysfunction is persistent—particularly when combined with high blood pressure, diabetes, high cholesterol, smoking, obesity or a family history of cardiovascular disease—consider discussing both your sexual health and cardiovascular risk with a qualified healthcare professional. Treating ED should not only be about improving erections. In some cases, it may also provide an opportunity to identify and manage an important underlying health problem earlier. Frequently Asked Questions 1.Can erectile dysfunction happen before a heart attack? It can. In some men, vascular ED develops several years before clinically apparent coronary artery disease or cardiovascular events. However, ED does not mean that a heart attack is inevitable. 2.How many years before heart disease can ED appear? Clinical guidance describes an interval of roughly 2–5 years between ED and some forms of clinically apparent cardiovascular disease in certain men. 3.Does ED always mean clogged arteries? No. ED can result from psychological issues, hormonal problems, medications, diabetes, neurological disorders and many other causes. 4.Should young men with ED get their heart checked? Persistent unexplained ED in a younger man should be discussed with a healthcare professional. Cardiovascular risk assessment may be appropriate even when there are no obvious heart symptoms. 5.Can high cholesterol cause erectile dysfunction? High cholesterol may contribute to atherosclerosis and endothelial dysfunction, which can reduce blood flow to the penis and contribute to ED. 6.Can high blood pressure cause ED? Yes. Long-term hypertension can damage blood vessels and reduce circulation. Some blood-pressure medicines may also contribute to ED, although medication should never be stopped without medical advice. 7.Can improving cardiovascular health improve erections? It may. Regular exercise, smoking cessation, weight management, healthy eating and good control of blood pressure, cholesterol and diabetes can support both cardiovascular and erectile health. 8.Can I take sildenafil if I have heart disease? Some people with stable cardiovascular disease can use sildenafil, but medical assessment may be necessary. Sildenafil and other PDE5 inhibitors must not be combined with nitrate medicines used for angina because the combination can cause a dangerous drop in blood pressure.
Dr. Marcus Vance, PharmD
Erectile Dysfunctiion
Erectile Dysfunction but Normal Testosterone: What Else Could Be Causing It?
Erectile dysfunction (ED) is often associated with low testosterone, but testosterone is only one part of the erection process. A man can have testosterone levels within the normal range and still experience difficulty getting or maintaining an erection. An erection depends on the coordinated function of the brain, blood vessels, nerves, hormones, muscles and emotions . A problem affecting any one of these systems can contribute to erectile dysfunction. For this reason, normal testosterone results should not automatically end the investigation into persistent ED. This article explains some of the most important causes doctors may consider when erectile dysfunction occurs despite normal testosterone levels. Does Normal Testosterone Rule Out Erectile Dysfunction? No. Testosterone contributes to libido, sexual function and overall reproductive health, but normal testosterone does not guarantee normal erections. Erectile dysfunction is commonly related to vascular, neurological, metabolic, medication-related and psychological factors , and many men have more than one contributing cause at the same time. Current European urology guidance describes ED as commonly having a mixed rather than purely hormonal, physical or psychological cause. Therefore, someone can have completely normal testosterone levels while experiencing significant ED. 1. Reduced Blood Flow to the Penis One of the most important causes of erectile dysfunction is inadequate blood flow. During sexual stimulation, arteries supplying the penis need to widen so that enough blood can enter the erectile tissue. Conditions that damage blood vessels or reduce their ability to dilate can interfere with this process. Possible contributors include: High blood pressure High cholesterol Atherosclerosis Diabetes Obesity Metabolic syndrome Smoking These conditions may affect erectile function even when testosterone is normal. 1. ED May Sometimes Be a Cardiovascular Warning Sign Persistent ED deserves attention because erectile problems can sometimes appear before more obvious symptoms of cardiovascular disease. The Princeton IV cardiovascular consensus, summarized by the American College of Cardiology, considers ED an important cardiovascular risk marker, particularly when the ED appears to have a vascular cause. This doesn't mean that every man with ED has heart disease. However, unexplained ED may provide an opportunity to check cardiovascular risk factors such as blood pressure, cholesterol, blood sugar and smoking status. 2. Diabetes or Prediabetes Diabetes is another major cause of erectile dysfunction. Chronically elevated blood glucose can damage both the blood vessels and nerves involved in erections. NIDDK notes that diabetes-related vascular and nerve damage can lead to sexual dysfunction. In some men, ED may occur before diabetes has been diagnosed. Possible signs that may warrant blood-glucose testing include: Increased thirst Frequent urination Unexplained fatigue Being overweight Family history of diabetes High blood pressure High triglycerides Doctors may therefore check fasting glucose or HbA1c when evaluating ED. Current European Association of Urology guidance recommends assessing glucose or HbA1c and a lipid profile when appropriate as part of the basic ED evaluation. 3. High Cholesterol and Metabolic Syndrome High cholesterol may gradually damage arteries and interfere with healthy blood flow. Metabolic syndrome—a combination of problems such as abdominal obesity, high blood pressure, abnormal cholesterol and impaired glucose regulation—is also associated with ED. A man may therefore have normal testosterone but still develop erectile difficulties because the vascular system supplying the penis is not functioning optimally. 4. Certain Medications Some commonly prescribed medicines can contribute to erectile difficulties. Medications associated with ED may include certain: Antidepressants Blood pressure medications Diuretics Antihistamines Sedatives Pain medications Hormonal treatments Some medicines used for prostate conditions NIDDK includes several of these medication groups among drugs that may contribute to ED. However, never stop a prescribed medication simply because you suspect it is affecting erections . A healthcare professional can review the medication, dosage and alternatives and determine whether a treatment change is appropriate. 5. Stress and Performance Anxiety Not all erectile dysfunction is caused by a physical abnormality. Stress can significantly affect sexual performance. For example, a man may experience one episode of difficulty maintaining an erection. He then becomes worried that it will happen again. That worry increases anxiety during sexual activity, which may make another erection problem more likely. Over time, this can create a cycle of: Erection difficulty → worry about performance → increased anxiety → further erection difficulty. Stress, anxiety and other emotional factors are recognized contributors to ED. 6. Depression and Other Mental Health Conditions Depression may reduce sexual desire and interfere with the brain signals involved in sexual arousal. Anxiety, low self-esteem and relationship difficulties can also contribute. Importantly, psychological and physical causes can exist together. For example, mild vascular ED could trigger performance anxiety, which then makes the original erectile problem more noticeable. Counseling or psychological therapy may therefore be helpful when emotional or relationship factors are contributing to ED. 7. Nerve Problems Normal erections require healthy communication between the brain, spinal cord and nerves supplying the penis. Neurological problems affecting this pathway may result in ED even when testosterone levels are normal. Possible causes include: Multiple sclerosis Parkinson's disease Spinal cord injury Stroke Diabetic neuropathy Peripheral neuropathy Nerve damage following pelvic surgery Both NIDDK and European urology guidelines recognize neurological disorders and nerve injuries as possible causes of ED. 8. Previous Pelvic or Prostate Surgery Operations involving the prostate, bladder, rectum or surrounding pelvic structures can sometimes affect the nerves or blood vessels required for erections. Erectile problems may therefore occur following treatments such as: Radical prostatectomy Pelvic cancer surgery Pelvic radiotherapy Certain urethral procedures The likelihood and degree of recovery vary considerably depending on the procedure, age, baseline erectile function and whether nerves could be preserved. 9. Peyronie's Disease or Structural Problems Peyronie's disease occurs when fibrous scar tissue develops inside the penis. It may cause: Penile curvature Pain during erection Shortening Narrowing or indentation Difficulty with intercourse Erectile dysfunction A physical examination during an ED evaluation can help identify Peyronie's disease and other structural abnormalities. 10. Smoking Smoking is strongly associated with blood-vessel damage. Because erections depend heavily on healthy circulation, long-term tobacco exposure can impair blood flow to the penis. NIDDK recommends smoking cessation as part of improving erectile and overall cardiovascular health. Stopping smoking can therefore be an important part of an ED treatment strategy even when testosterone is normal. 11. Excessive Alcohol or Recreational Drug Use Heavy alcohol consumption and recreational drug use may affect the nervous system, circulation and sexual response. Alcohol can also reduce sexual performance temporarily, while long-term excessive intake may contribute to broader health problems associated with ED. Both NIDDK and Mayo Clinic list excessive alcohol or illicit drug use among possible contributors to erectile difficulties. 12. Obesity and Physical Inactivity Being overweight or obese is associated with multiple ED risk factors, including: Diabetes High blood pressure High cholesterol Vascular dysfunction Metabolic syndrome Lack of regular physical activity is also associated with ED. Exercise, weight management and cardiovascular risk reduction may therefore form an important part of treatment. 13. Sleep Problems Sleep disorders can also affect sexual health. Poor-quality sleep may influence cardiovascular function, energy, mental health and hormonal regulation. Mayo Clinic includes sleep conditions among possible physical contributors to ED. Someone experiencing ED together with symptoms such as loud snoring, severe daytime sleepiness or witnessed pauses in breathing during sleep should discuss those symptoms with a healthcare professional. 14. Your Total Testosterone May Be Normal, but Further Hormonal Assessment Could Occasionally Be Needed A single "normal testosterone" result does not answer every hormonal question. Testosterone varies throughout the day, and interpretation can depend on: Time the blood sample was collected Total testosterone level Sex hormone-binding globulin (SHBG) Free or bioavailable testosterone Symptoms Other endocrine conditions European urology guidance recommends early-morning total testosterone during ED assessment and notes that calculated free or bioavailable testosterone may sometimes help clarify the result. Other hormonal problems, such as thyroid abnormalities, may occasionally contribute to sexual dysfunction as well. This does not mean everyone with ED needs extensive hormone testing. Additional testing should be guided by symptoms and a healthcare professional's evaluation. How Do Doctors Investigate ED When Testosterone Is Normal? Evaluation usually involves looking beyond testosterone. A healthcare professional may ask about: When the erectile problems started Whether ED happens every time or only occasionally Morning or nighttime erections Sexual desire Ejaculation and orgasm Current medications Alcohol, smoking and recreational drugs Diabetes and cardiovascular risk factors Stress, anxiety and relationship factors Previous surgery or injuries A physical examination may assess the cardiovascular, neurological, hormonal and genital systems. Depending on the individual, blood tests may include: Fasting glucose or HbA1c Cholesterol and triglycerides Morning testosterone Thyroid testing when indicated Additional hormonal tests when clinically appropriate Specialized testing such as penile Doppler ultrasound, nighttime erection testing or other vascular investigations is generally reserved for selected cases. Can ED With Normal Testosterone Be Treated? Yes. Treatment depends on the underlying cause rather than simply trying to raise testosterone. Management may include: Lifestyle Changes Depending on individual risk factors, doctors may recommend: Regular physical activity Weight management Smoking cessation Limiting excessive alcohol Better diabetes control Managing cholesterol Treating high blood pressure Improving sleep These measures can support both cardiovascular and erectile health. Reviewing Current Medicines If a medication appears to contribute to ED, a healthcare professional may consider adjusting the dosage or choosing an alternative where appropriate. Do not make these changes without medical supervision. PDE5 Inhibitors Common prescription ED medicines include: Sildenafil Tadalafil Vardenafil Avanafil These phosphodiesterase type 5 (PDE5) inhibitors increase blood flow to the penis in response to sexual stimulation. They are not suitable for everyone. PDE5 inhibitors should not be combined with nitrate medications , because the combination can cause a dangerous fall in blood pressure. Cardiovascular health and other medications should therefore be reviewed before treatment. Psychological or Sex Therapy When anxiety, depression, stress or relationship difficulties are contributing to ED, counseling or psychosexual therapy may help. In mixed ED, psychological treatment may be combined with medical treatment. Other ED Treatments When tablets are inappropriate or ineffective, treatment options may include: Vacuum erection devices Penile injections Intraurethral treatment Penile implants in selected cases The appropriate treatment depends on the cause, severity, medical history and patient preference. Should You Take Testosterone if Your Testosterone Level Is Normal? Testosterone therapy should not be used simply because a person has erectile dysfunction . If testosterone levels are genuinely normal and there are no other indications for testosterone treatment, increasing testosterone may not address the actual cause of the ED. Instead, evaluation should focus on factors such as circulation, metabolic health, medications, neurological conditions and psychological health. Testosterone treatment should only be considered following proper clinical and laboratory assessment. When Should You See a Doctor? Occasional erection difficulty can happen to many men. Medical evaluation becomes particularly important when ED: Happens repeatedly Persists for several weeks or months Is becoming progressively worse Occurs alongside reduced exercise tolerance or cardiovascular symptoms Is associated with diabetes or significant cardiovascular risk factors Starts after a new medication Follows pelvic surgery or injury Causes significant anxiety or relationship problems Persistent ED should not simply be dismissed as aging or a testosterone problem. Frequently Asked Questions 1. Can you have ED with normal testosterone? Yes. Many causes of erectile dysfunction—including vascular disease, diabetes, medications, neurological problems, stress and anxiety—can occur while testosterone remains within the normal range. 2. Does normal testosterone mean the ED is psychological? No. Normal testosterone does not prove that erectile dysfunction is psychological. Blood-vessel, neurological, metabolic, structural and medication-related causes remain possible. 3. Can poor circulation cause ED even with normal testosterone? Yes. Reduced arterial blood flow is an important cause of erectile dysfunction and can occur independently of testosterone levels. 4. Can stress cause ED when testosterone is normal? Yes. Stress and performance anxiety can interfere with the brain's sexual response and may cause or worsen erectile difficulties. 5. What blood tests are commonly checked for ED? Depending on the person's history, assessment may include glucose or HbA1c, cholesterol and triglycerides, morning testosterone and selected additional tests such as thyroid or other hormone measurements. 6. Can ED be an early sign of heart disease? ED can be associated with underlying cardiovascular disease, particularly when its cause appears vascular. Current cardiovascular guidance recognizes ED as a cardiovascular risk marker, although having ED does not mean that a person definitely has heart disease. The Bottom Line Having normal testosterone does not mean erectile dysfunction should be ignored. Testosterone is only one component of healthy erectile function. Blood circulation, nerves, blood sugar, cardiovascular health, medications, lifestyle, psychological health and structural problems can all affect erections. For men experiencing persistent ED despite normal testosterone, the next step is usually not trying to increase testosterone. Instead, a healthcare professional should look for the underlying cause and any potentially modifiable risk factors. Identifying that cause is important not only for sexual health but also because, in some men, ED can provide an early opportunity to detect diabetes, cardiovascular risk factors or other medical conditions.
Dr. Marcus Vance, PharmD
Erectile Dysfunctiion
Can you take erectile dysfunction medicine every day?
The answer is yes in some cases—but it depends on the medicine, dose, your health, and other medications you take. Tadalafil is the best-known ED medicine that can be prescribed specifically as a low-dose once-daily treatment . Other ED medicines are generally used on an as-needed basis and should not automatically be turned into a daily treatment without medical advice. This article explains how daily ED treatment works, who may benefit, possible side effects, important drug interactions, and when daily treatment may not be appropriate. What Are Erectile Dysfunction Medicines? The most commonly used oral ED medicines belong to a group called phosphodiesterase type 5 inhibitors, or PDE5 inhibitors . They include: Tadalafil (Cialis) Sildenafil (Viagra) Vardenafil Avanafil (Stendra) These medicines increase the effect of nitric oxide, helping relax smooth muscle and improve blood flow to the penis. They do not automatically cause an erection . Sexual stimulation is still required for them to work. Can You Take ED Medicine Every Day? Potentially, yes. However, taking an ED medicine once every day is different from taking an as-needed tablet every day simply because sexual activity occurs frequently . The treatment must be selected according to the particular medication and dose. Tadalafil Can Be Prescribed for Daily Use Tadalafil has an established once-daily treatment regimen for erectile dysfunction. For daily ED treatment, the recommended starting tadalafil dose in U.S. prescribing information is: Tadalafil 2.5 mg once daily Depending on effectiveness and tolerability, a healthcare provider may increase this to: Tadalafil 5 mg once daily It should generally be taken at approximately the same time every day, regardless of when sexual activity is expected. This is different from as-needed tadalafil, where doses such as 10 mg or 20 mg may be prescribed before anticipated sexual activity. Why Would Someone Take Tadalafil Every Day? Daily tadalafil may be useful for men who want greater spontaneity rather than planning medication around sexual activity. Because tadalafil remains active in the body longer than many other PDE5 inhibitors, maintaining a low daily level of the medicine means sexual activity does not need to be timed as closely to taking a tablet. Potential advantages include: Less need to plan medication before sex Greater spontaneity Continuous availability of ED treatment A lower individual dose than typical as-needed treatment Treatment of ED in men who have relatively frequent sexual activity Possible additional benefit in men who also have symptoms of benign prostatic hyperplasia (BPH) Tadalafil 5 mg once daily is also used for men who have both erectile dysfunction and symptoms of an enlarged prostate . Daily Tadalafil vs Tadalafil as Needed Both approaches can be effective, but they are used differently. Daily Tadalafil A low dose is taken every day, whether or not sexual activity is planned. Typical regimen: 2.5 mg once daily , potentially increased to 5 mg once daily based on response and tolerability. As-Needed Tadalafil Tadalafil may instead be taken before anticipated sexual activity. A commonly recommended starting dose is: 10 mg before sexual activity The dose may be reduced to 5 mg or increased to 20 mg depending on response and tolerability. Tadalafil can improve erectile function for up to approximately 36 hours after a dose , which is much longer than many other ED medicines. Taking a 10 mg or 20 mg tadalafil tablet every day should not be assumed to be equivalent to prescribed low-dose daily tadalafil. Your healthcare provider should determine the appropriate regimen. Can You Take Sildenafil Every Day? Sildenafil is generally prescribed for erectile dysfunction on an as-needed basis . For ED, sildenafil is commonly taken before anticipated sexual activity and should generally not be taken more than once in a 24-hour period . That does not mean everyone should automatically take sildenafil every day. The frequency and dose may need adjustment depending on: Age Kidney function Liver function Other medications Blood pressure Cardiovascular health Side effects Response to treatment If you find yourself needing sildenafil very frequently, speak with a healthcare provider about whether your current treatment or a daily tadalafil regimen may be more appropriate. What About Vardenafil and Avanafil? Vardenafil and avanafil are also PDE5 inhibitors. They are generally used when needed before sexual activity , rather than as routine low-dose daily treatments for ED. The medicines differ in how quickly they start working, how long their effects last, their interactions, and their side-effect profiles. Do not switch from one ED medicine to another—or combine them—without medical guidance. Is Daily ED Medicine Safe Long Term? For appropriately selected patients, PDE5 inhibitors can be used over extended periods under medical supervision. The key issue is not simply how long the medicine is taken. Safety depends heavily on: Your cardiovascular health Blood pressure Kidney function Liver function Other medications The ED medicine being used The dose How frequently it is taken Regular medical review is particularly important when ED is persistent because erection problems may sometimes be associated with underlying conditions such as diabetes, cardiovascular disease, high blood pressure, hormonal abnormalities, or medication side effects. Common Side Effects of Daily ED Medicines PDE5 inhibitors are generally well tolerated, but side effects can occur. Common effects may include: Headache Facial flushing Indigestion Nasal congestion Dizziness Muscle aches Back pain Tadalafil is particularly associated with back pain and muscle aches in some users. Side effects may become more noticeable if too much medication is taken or ED medicines are combined incorrectly. Who Should Not Take ED Medicines Every Day? Daily ED treatment is not appropriate for everyone. You should discuss ED medicine with a healthcare professional before treatment if you have: Heart disease Previous heart attack Previous stroke Very low blood pressure Uncontrolled high blood pressure Severe kidney disease Severe liver disease Certain inherited eye disorders A history of serious reactions to PDE5 inhibitors Your healthcare provider should also review all prescription medicines, over-the-counter products, and supplements you use. Never Combine ED Medicines With Nitrates One of the most important ED medicine safety rules involves nitrates . PDE5 inhibitors such as tadalafil and sildenafil should not be combined with nitrate medicines commonly used to treat angina or chest pain. Examples include: Nitroglycerin Isosorbide mononitrate Isosorbide dinitrate Combining nitrates with PDE5 inhibitors can cause a dangerous fall in blood pressure . Tadalafil should also not be used with the pulmonary-hypertension medicine riociguat . Always tell doctors and emergency medical staff when you last took an ED medicine if you develop chest pain. What About ED Medicines and Alpha-Blockers? Alpha-blockers may be prescribed for conditions including enlarged prostate or high blood pressure. Using an alpha-blocker together with a PDE5 inhibitor can sometimes lower blood pressure excessively. That does not necessarily mean the medicines can never be used together, but the combination requires careful consideration of the medications, doses, blood pressure and overall health. Can You Combine Two Erectile Dysfunction Medicines? You should not combine PDE5 inhibitors on your own . For example, do not take: Sildenafil plus tadalafil Tadalafil plus vardenafil Sildenafil plus avanafil Combining treatments can increase the risk of: Low blood pressure Dizziness Headache Flushing Priapism Other adverse effects If one ED medication is not working adequately, the safer approach is to speak with a healthcare provider about adjusting the dose, timing, medication or overall treatment strategy. Does Taking ED Medicine Daily Cause Dependence? PDE5 inhibitors are not generally considered physically addictive medicines. However, some men may become psychologically reliant on having medication available before sexual activity, particularly when performance anxiety contributes to ED. If erections were previously normal but you increasingly feel unable to have sex without medication, it may be worth discussing both physical and psychological factors with a healthcare professional. Does Daily Tadalafil Increase Sexual Desire? No. Tadalafil improves the physiological process that allows increased blood flow to the penis. It does not directly increase testosterone or sexual desire , and it does not cause an erection without sexual stimulation. If low libido rather than erection quality is the main problem, other factors such as testosterone levels, stress, depression, medications, sleep problems or relationship issues may need evaluation. When Should You Seek Medical Attention? Most side effects are mild, but certain symptoms require urgent medical attention. Seek urgent medical care if you experience: An erection lasting more than 4 hours Sudden loss or major reduction of vision Sudden hearing loss Severe dizziness or fainting Chest pain Severe shortness of breath An erection lasting longer than four hours—called priapism —requires prompt medical treatment to reduce the risk of permanent tissue damage. Is Daily ED Medicine Better Than Taking It Only When Needed? Neither approach is automatically better. Daily treatment may suit someone who: Has sex relatively frequently Wants more spontaneity Does not want to plan medication before sex Responds well to low-dose tadalafil Has both ED and BPH symptoms As-needed treatment may suit someone who: Has sex less frequently Prefers taking medication only when necessary Responds well to sildenafil, tadalafil, avanafil or vardenafil before sexual activity Does not want to take medication every day Your medical history, preferences, frequency of sexual activity and response to treatment should guide the decision. Frequently Asked Questions 1.Can I take tadalafil every day? Yes. Tadalafil can be prescribed specifically for once-daily treatment of erectile dysfunction . A commonly recommended starting dose is 2.5 mg once daily , which may be increased to 5 mg once daily depending on effectiveness and tolerability. 2.Can I take tadalafil 20 mg every day? A 20 mg dose is generally associated with as-needed ED treatment rather than the standard once-daily ED regimen . Do not convert an as-needed prescription into daily use without speaking with your healthcare provider. 3.Can I take sildenafil every day? Sildenafil for ED is generally taken as needed and should not normally be taken more than once in a 24-hour period. Whether frequent use is appropriate should be discussed with a healthcare provider. 4.Can I take ED medication even if I do not have erectile dysfunction? ED medicines are prescription treatments intended for specific medical indications. People who can obtain and maintain normal erections generally do not need them, and taking medication unnecessarily still exposes you to side effects and drug interactions. 5.Does daily tadalafil give you a constant erection? No. Tadalafil does not create a continuous erection. Sexual stimulation is still required for an erection to occur. 6.Can daily tadalafil also help an enlarged prostate? Yes. Tadalafil 5 mg once daily is used for symptoms of benign prostatic hyperplasia and for men who have both BPH and erectile dysfunction. The Bottom Line Some erectile dysfunction medicines can be taken every day, but the medicine and dose matter. Tadalafil is the main PDE5 inhibitor with an established low-dose daily regimen for ED. Daily treatment usually involves 2.5 mg or 5 mg tadalafil , rather than repeatedly taking higher as-needed doses. Sildenafil, vardenafil and avanafil are generally used around anticipated sexual activity rather than automatically taken as routine daily ED treatment. Most importantly, ED medicines should never be combined casually, and they can be dangerous when used with nitrates or certain other medicines. If you need ED medication frequently, have persistent erectile difficulties, or notice that your usual treatment no longer works well, speak with a healthcare professional. Persistent ED may also provide an opportunity to check for cardiovascular, metabolic, hormonal or medication-related causes.
Dr. Marcus Vance, PharmD
Anabolic Steriod
Oral vs Injectable Anabolic Steroids: How Do Health Risks Differ?
Anabolic-androgenic steroids (AAS) are synthetic substances related to testosterone. Although some anabolic steroids have legitimate medical uses, nonmedical use for muscle growth, strength, or appearance can expose the body to significant health risks. What Are Oral Anabolic Steroids? Oral anabolic steroids are formulated so they can be swallowed and absorbed through the gastrointestinal tract. Many oral AAS are chemically modified at the 17-alpha position . This modification allows the steroid to survive metabolism sufficiently to remain active when taken by mouth. Examples of 17-alpha-alkylated anabolic steroids include compounds such as oxandrolone, stanozolol and oxymetholone. The same structural modification that improves oral activity is also associated with greater potential for liver toxicity. LiverTox notes that 17-alpha-alkylated androgenic steroids have been associated with cholestatic liver injury, peliosis hepatis and liver tumors. What Are Injectable Anabolic Steroids? Injectable anabolic steroids are generally administered into muscle. Many are testosterone or testosterone-like compounds modified with an ester that allows the hormone to remain active for longer periods. Because these drugs do not need the same chemical modification required by many oral steroids, some injectable preparations are less strongly associated with cholestatic liver injury than 17-alpha-alkylated oral steroids. However, this does not mean injectable steroids are harmless. Injectable AAS can still affect blood pressure, cholesterol, heart structure, natural testosterone production, fertility, mood and other body systems. Nonsterile injections also introduce additional risks such as abscesses and transmission of blood-borne infections. Oral vs Injectable Steroids: Key Health-Risk Differences Health concern Oral anabolic steroids Injectable anabolic steroids Liver injury Often greater concern with 17-alpha-alkylated oral AAS Generally less cholestatic liver toxicity with many esterified preparations, but liver effects can still occur Cardiovascular risk Significant Significant Cholesterol changes Can be substantial Can also occur Blood-pressure effects Possible Possible Natural testosterone suppression Significant Significant Fertility problems Possible Possible Injection-site infection Not applicable Additional risk Abscess formation Not applicable Possible Blood-borne infection from shared equipment Not applicable Possible Counterfeit/contaminated products Possible Possible The route of administration changes some risks, but many of the most serious consequences of AAS exposure occur with both oral and injectable drugs . 1. Oral Steroids Usually Carry Greater Liver Concerns The most important difference between many oral and injectable anabolic steroids involves the liver. Many orally active anabolic steroids undergo 17-alpha alkylation so they are not rapidly broken down during first-pass metabolism. This modification can increase hepatotoxicity. Potential liver complications associated particularly with 17-alpha-alkylated anabolic steroids include cholestasis, jaundice, abnormal liver enzymes, peliosis hepatis and, with prolonged exposure, hepatic tumors. However, it would be inaccurate to say that every oral steroid causes liver damage or that injectable steroids cannot affect the liver. Risk varies considerably among individual drugs. 2. Both Routes Can Damage Cardiovascular Health One of the most important misconceptions surrounding injectable steroids is that avoiding oral steroids eliminates the major health dangers. It does not. AAS misuse has been associated with high blood pressure, harmful cholesterol changes, blood clots, heart attacks, stroke and structural changes to the heart . A recent systematic review and meta-analysis of athletes and physically active individuals found AAS exposure associated with higher blood pressure and adverse changes in LDL cholesterol, reinforcing concerns about cardiovascular health. These risks are related largely to the hormonal effects and exposure to anabolic steroids themselves rather than simply whether a drug is swallowed or injected. 3. Oral Steroids May Have Particularly Strong Effects on Cholesterol Some oral AAS can substantially worsen the blood-lipid profile, including reductions in protective HDL cholesterol and increases in LDL cholesterol. Injectable anabolic steroids can also produce unfavorable lipid changes, so switching routes should not be viewed as a reliable method of avoiding cardiovascular risk. A person's overall risk will depend on the compound, exposure level, duration, genetics, smoking, blood pressure and existing cardiovascular health. 4. Injectable Steroids Carry Injection-Specific Risks Injectable anabolic steroids introduce risks that oral steroids do not have. Poor injection technique or contaminated products can cause inflammation, tissue damage and bacterial infections. NIDA specifically identifies injection-site abscesses among possible complications associated with anabolic steroid misuse. Reusing or sharing needles or syringes can also transmit infections such as hepatitis B, hepatitis C and HIV . The CDC warns that unsafe injection practices can transmit viral, bacterial and fungal infections. 5. Both Can Suppress Natural Testosterone The body regulates testosterone through the hypothalamic-pituitary-gonadal axis. When high levels of external androgens are introduced, the brain can reduce signaling to the testes. As a result, natural testosterone production may fall substantially. Potential consequences include reduced testicular size, reduced sperm production, low testosterone after stopping AAS, reduced libido, erectile dysfunction and impaired fertility. Clinical reviews identify suppression of the gonadal axis and infertility among established adverse consequences of AAS exposure. This occurs with both oral and injectable steroids . 6. Fertility Can Be Affected Regardless of Route Men sometimes assume injectable testosterone or other injectable AAS will preserve fertility because the substance resembles naturally occurring testosterone. In reality, external androgens can suppress the hormones LH and FSH that stimulate the testes. Sperm production can consequently fall dramatically, sometimes resulting in severe oligospermia or temporary azoospermia. Recovery after discontinuation varies considerably between individuals, and sperm production may recover more slowly than circulating hormone levels. 7. Both Routes Can Increase Red Blood Cell Production Androgens can stimulate production of red blood cells. Excessive increases may lead to erythrocytosis , meaning an abnormally high concentration of red blood cells. Clinical literature identifies erythrocytosis as an established complication of AAS exposure, while high-dose use has also been associated with thrombotic and cardiovascular complications. This risk is not exclusive to one route of administration. 8. Psychological Effects Are Possible With Either Route Anabolic steroid exposure may also affect mood and behavior. Reported problems associated with misuse include irritability, mood changes, aggression, mania and, in some individuals, depression or anxiety—particularly during withdrawal after prolonged use. Again, these effects are related more to androgen exposure, dose and individual susceptibility than simply whether the steroid is oral or injectable. 9. Counterfeit Products Add Another Layer of Risk Nonmedical anabolic steroids are frequently obtained outside regulated medical supply chains. Products sold through unofficial sources may contain the wrong concentration, another substance entirely, contaminants or nonsterile ingredients. A 2024 clinical review noted that black-market androgen products may be counterfeit, adding uncertainty to the health risks associated with nonmedical AAS use. This concern applies to both tablets and injectable products. 10. Dose and Duration Matter More Than Route Alone It is tempting to ask which option is the "safer steroid." In reality, route is only one part of the risk profile . Health effects are influenced by the exact substance used, total androgen exposure, duration of use, use of multiple anabolic steroids or other substances, pre-existing medical conditions and individual susceptibility. A comprehensive review of AAS adverse effects notes that these drugs can contribute to hypertension, abnormal cholesterol, liver injury, testosterone deficiency, erectile dysfunction and cardiomyopathy. Using multiple substances together may make it even harder to predict which complications will occur. Are Injectable Steroids Safer for the Liver? In certain respects, many injectable esterified testosterone preparations have less potential for cholestatic liver injury than 17-alpha-alkylated oral anabolic steroids . LiverTox reports that 17-alpha-alkylated steroids are particularly associated with liver injury, whereas cholestasis has been reported much less commonly with 17-beta-esterified testosterone preparations. That difference should not be interpreted as meaning injectable steroids are generally safe. Liver toxicity represents only one part of the overall health risk of anabolic steroids . Which Is More Dangerous: Oral or Injectable Steroids? There is no simple answer. If the question is specifically about certain types of liver injury , many 17-alpha-alkylated oral anabolic steroids generally present the greater concern. If the question concerns infection or injection-site complications , injectable steroids introduce risks that oral preparations do not. For cardiovascular disease, testosterone suppression, infertility, sexual problems and psychological effects, both routes can carry significant risks . Therefore, comparing oral and injectable steroids solely by route can create a false sense of safety. When Should Someone Seek Medical Advice? Anyone currently using or who has recently stopped anabolic steroids should consider speaking openly with a healthcare professional, particularly if symptoms such as jaundice, severe abdominal pain, chest pain, shortness of breath, severe headache, leg swelling, persistent high blood pressure, reduced libido, erectile dysfunction , testicular shrinkage, infertility concerns, severe mood changes or injection-site redness and swelling develop. Chest pain, difficulty breathing, symptoms of stroke or severe infection require urgent medical attention. The Bottom Line Oral and injectable anabolic steroids have overlapping but somewhat different risk profiles. Many oral 17-alpha-alkylated steroids carry a greater risk of liver injury , while injectable steroids add risks related to infections, abscesses and unsafe needle practices. However, both forms can disrupt natural testosterone production, impair fertility, alter cholesterol and blood pressure and contribute to potentially serious cardiovascular and psychological complications. The most important message is that injectable anabolic steroids should not be considered a safe alternative to oral steroids . Route matters, but the specific drug, exposure level, duration and combination of substances often play an even larger role in determining overall health risk.
Dr. Marcus Vance, PharmD